

The history, people and purpose of Kids International Dental Services, with a particular focus on Cambodia
By Ian Kydd Miller — The Old Photographer
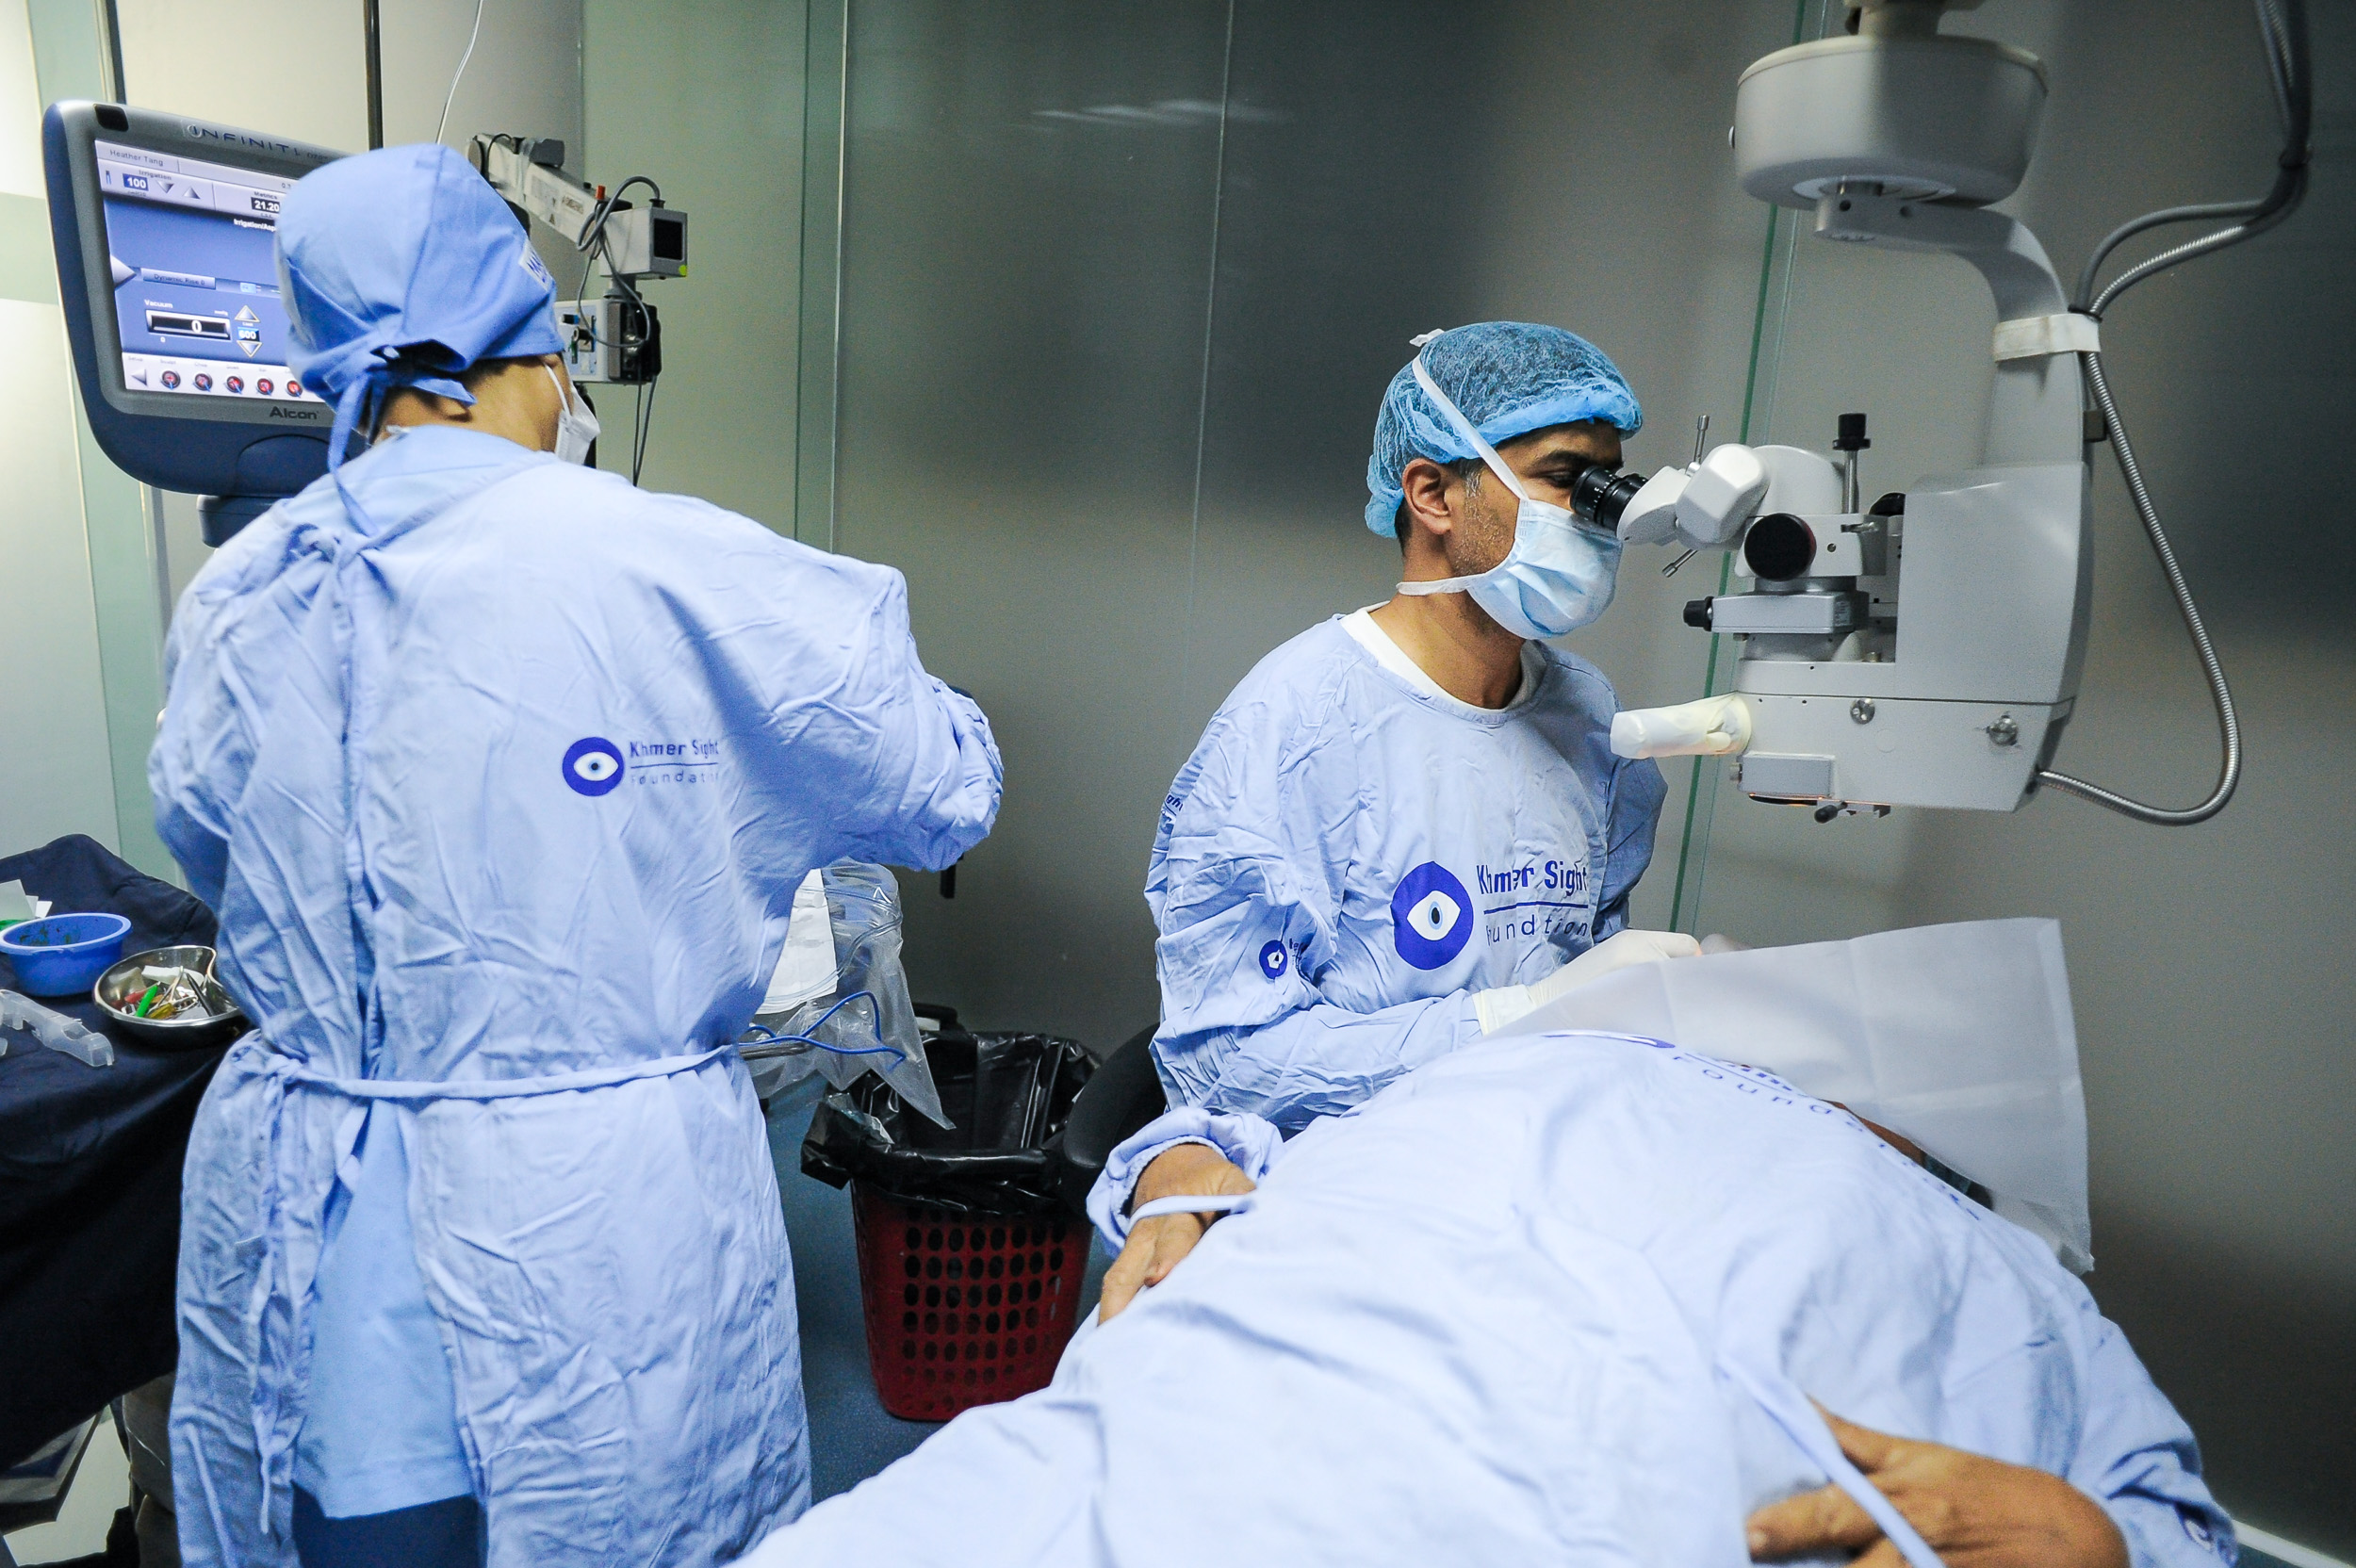
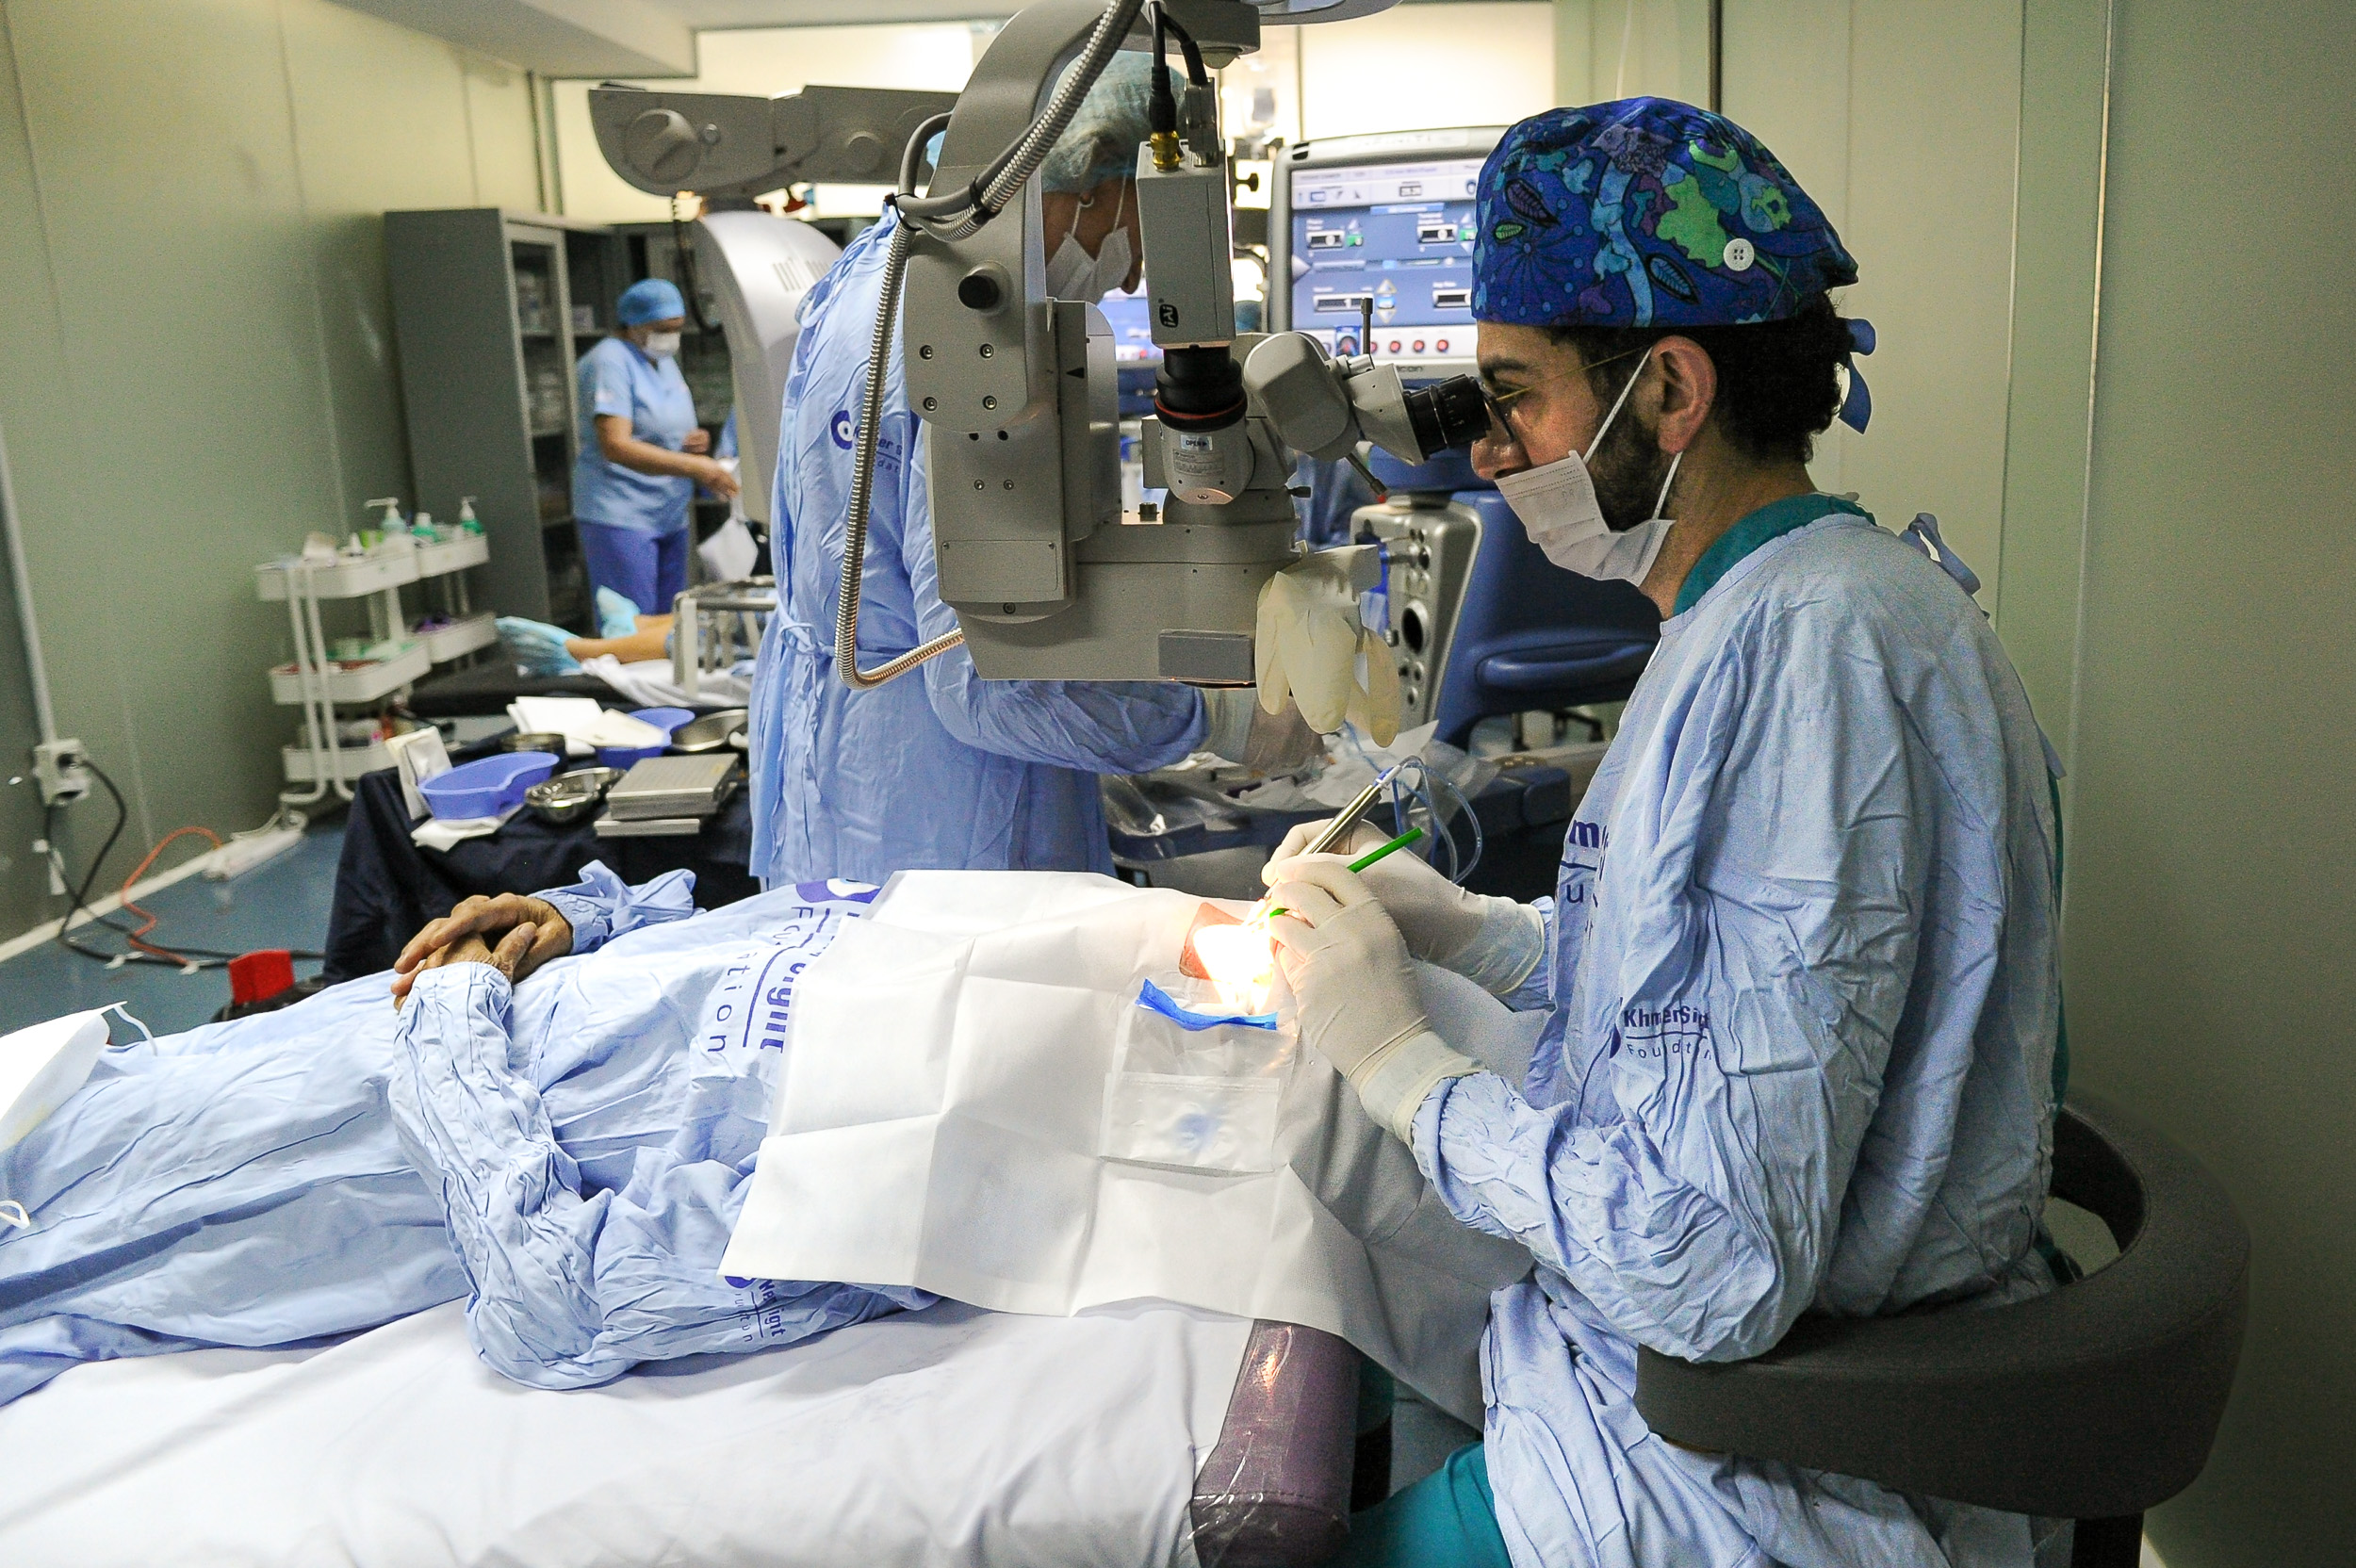
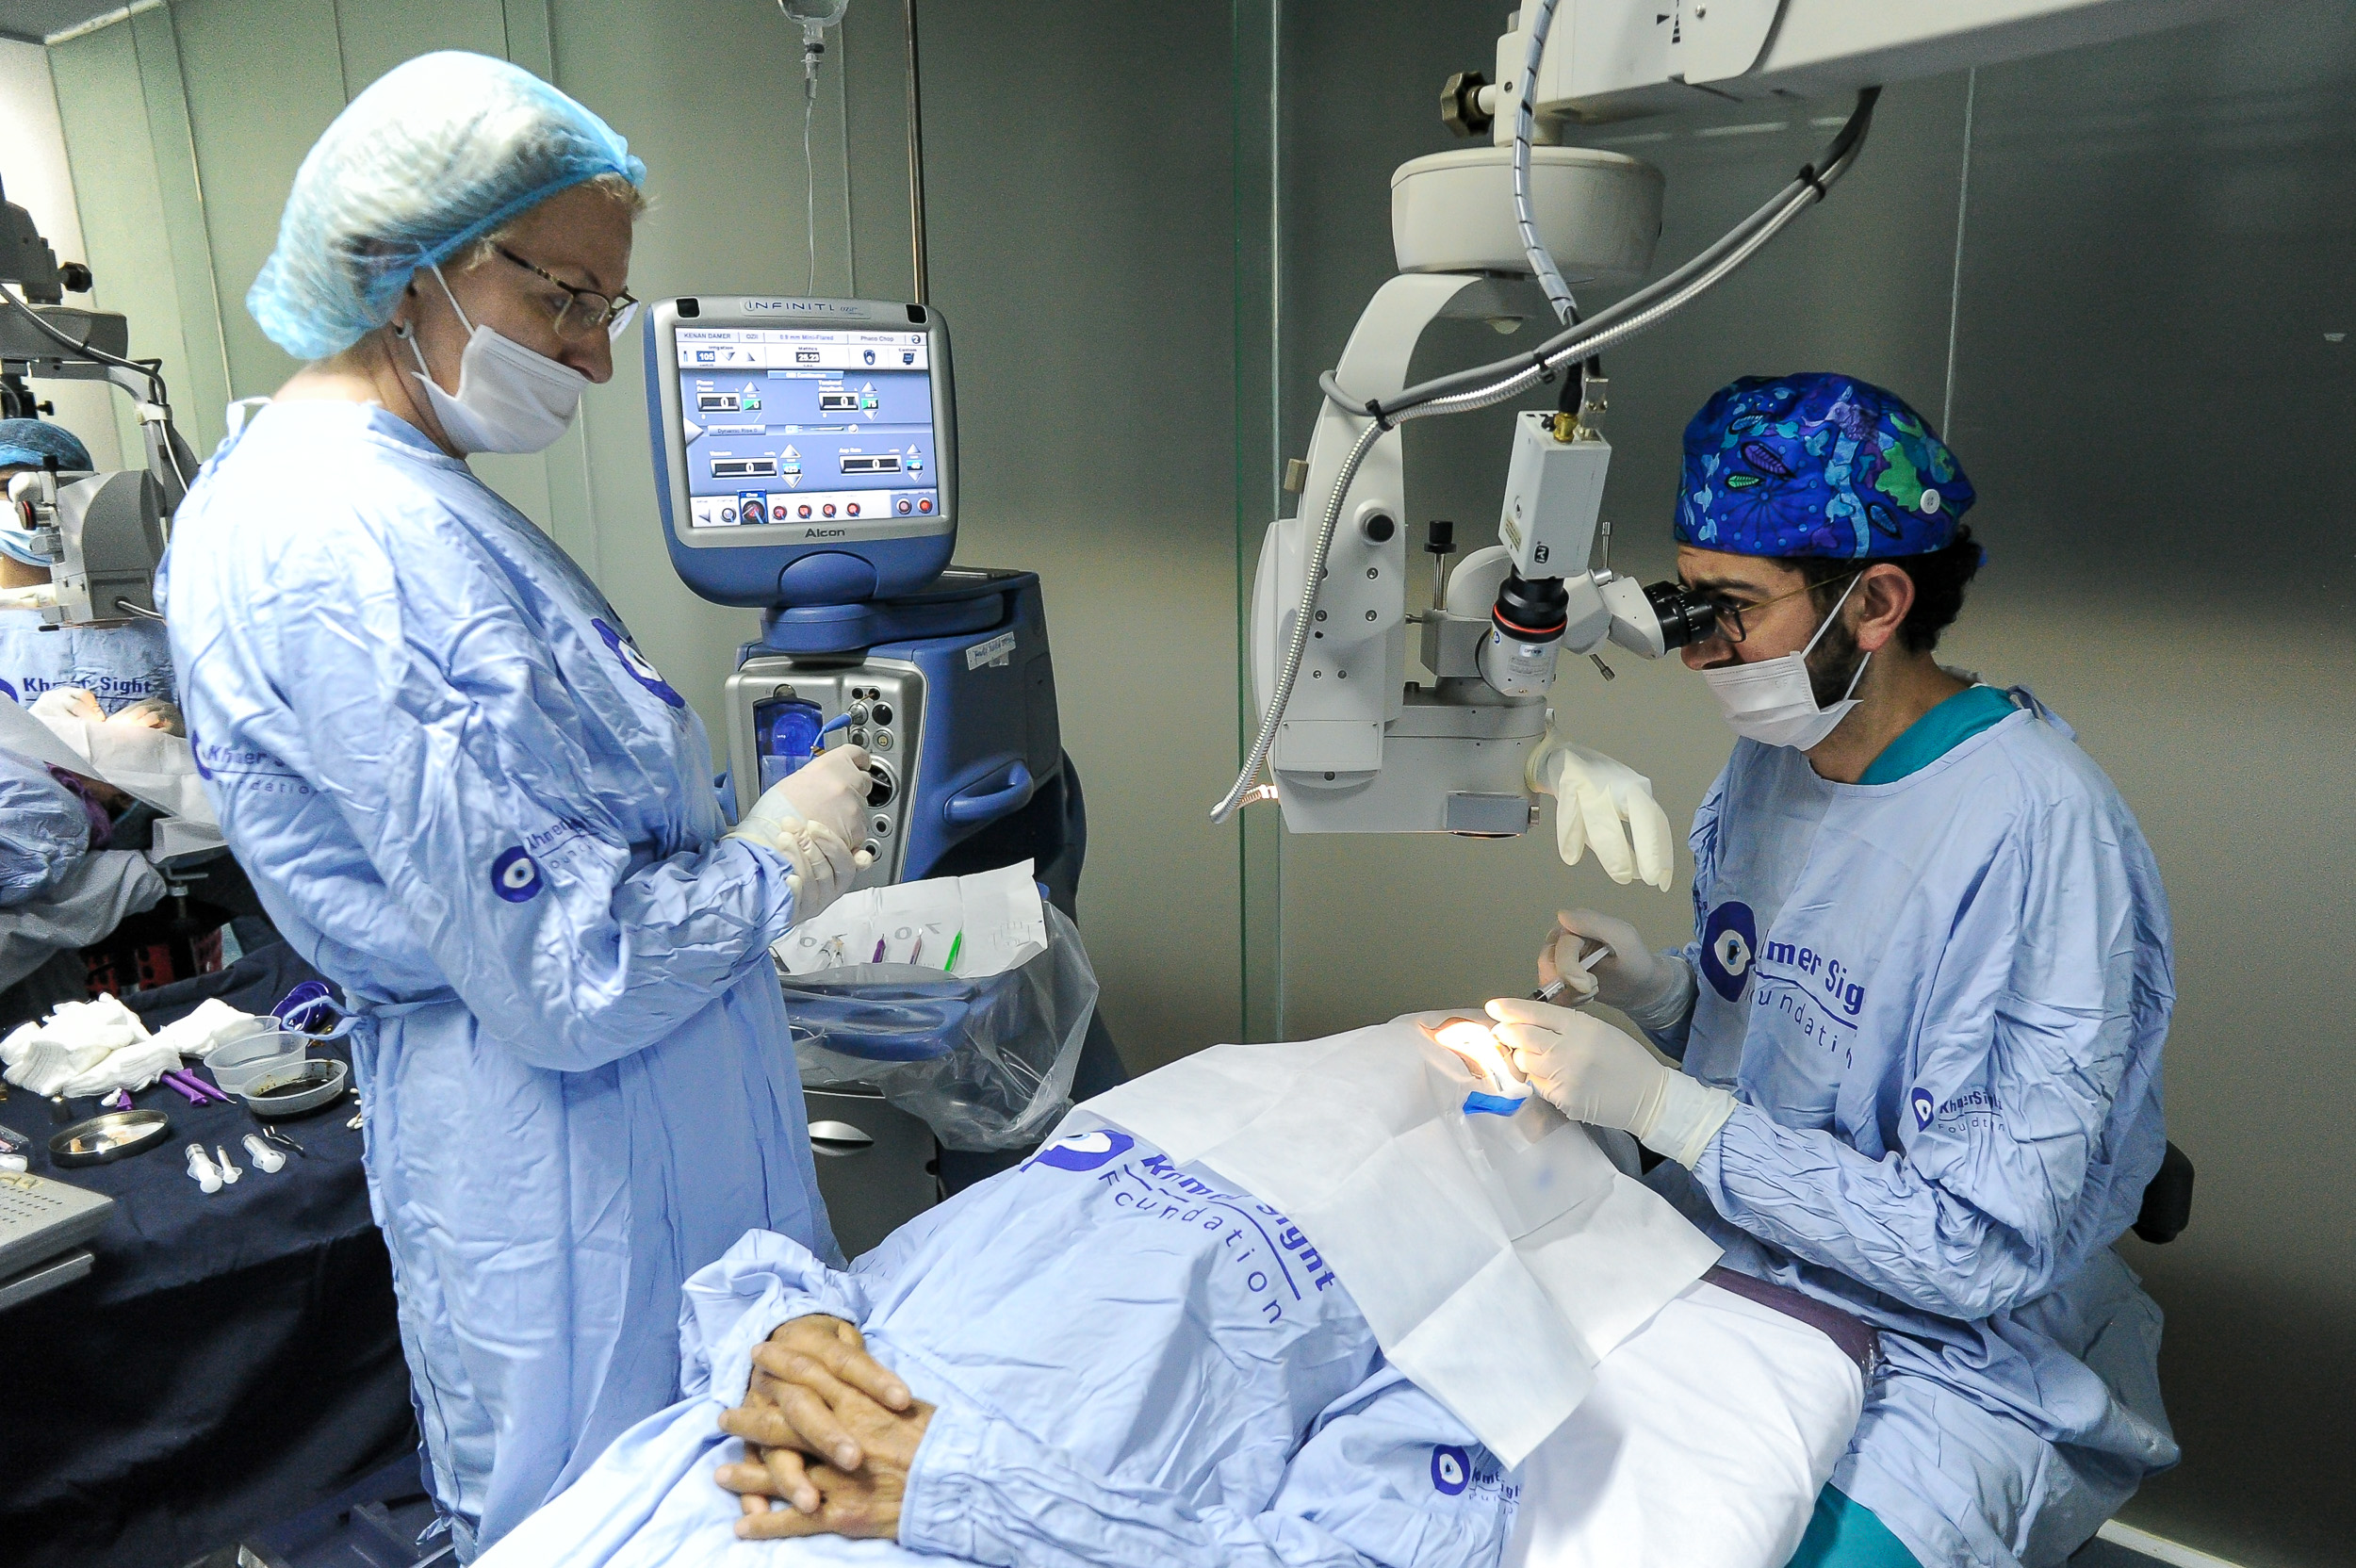
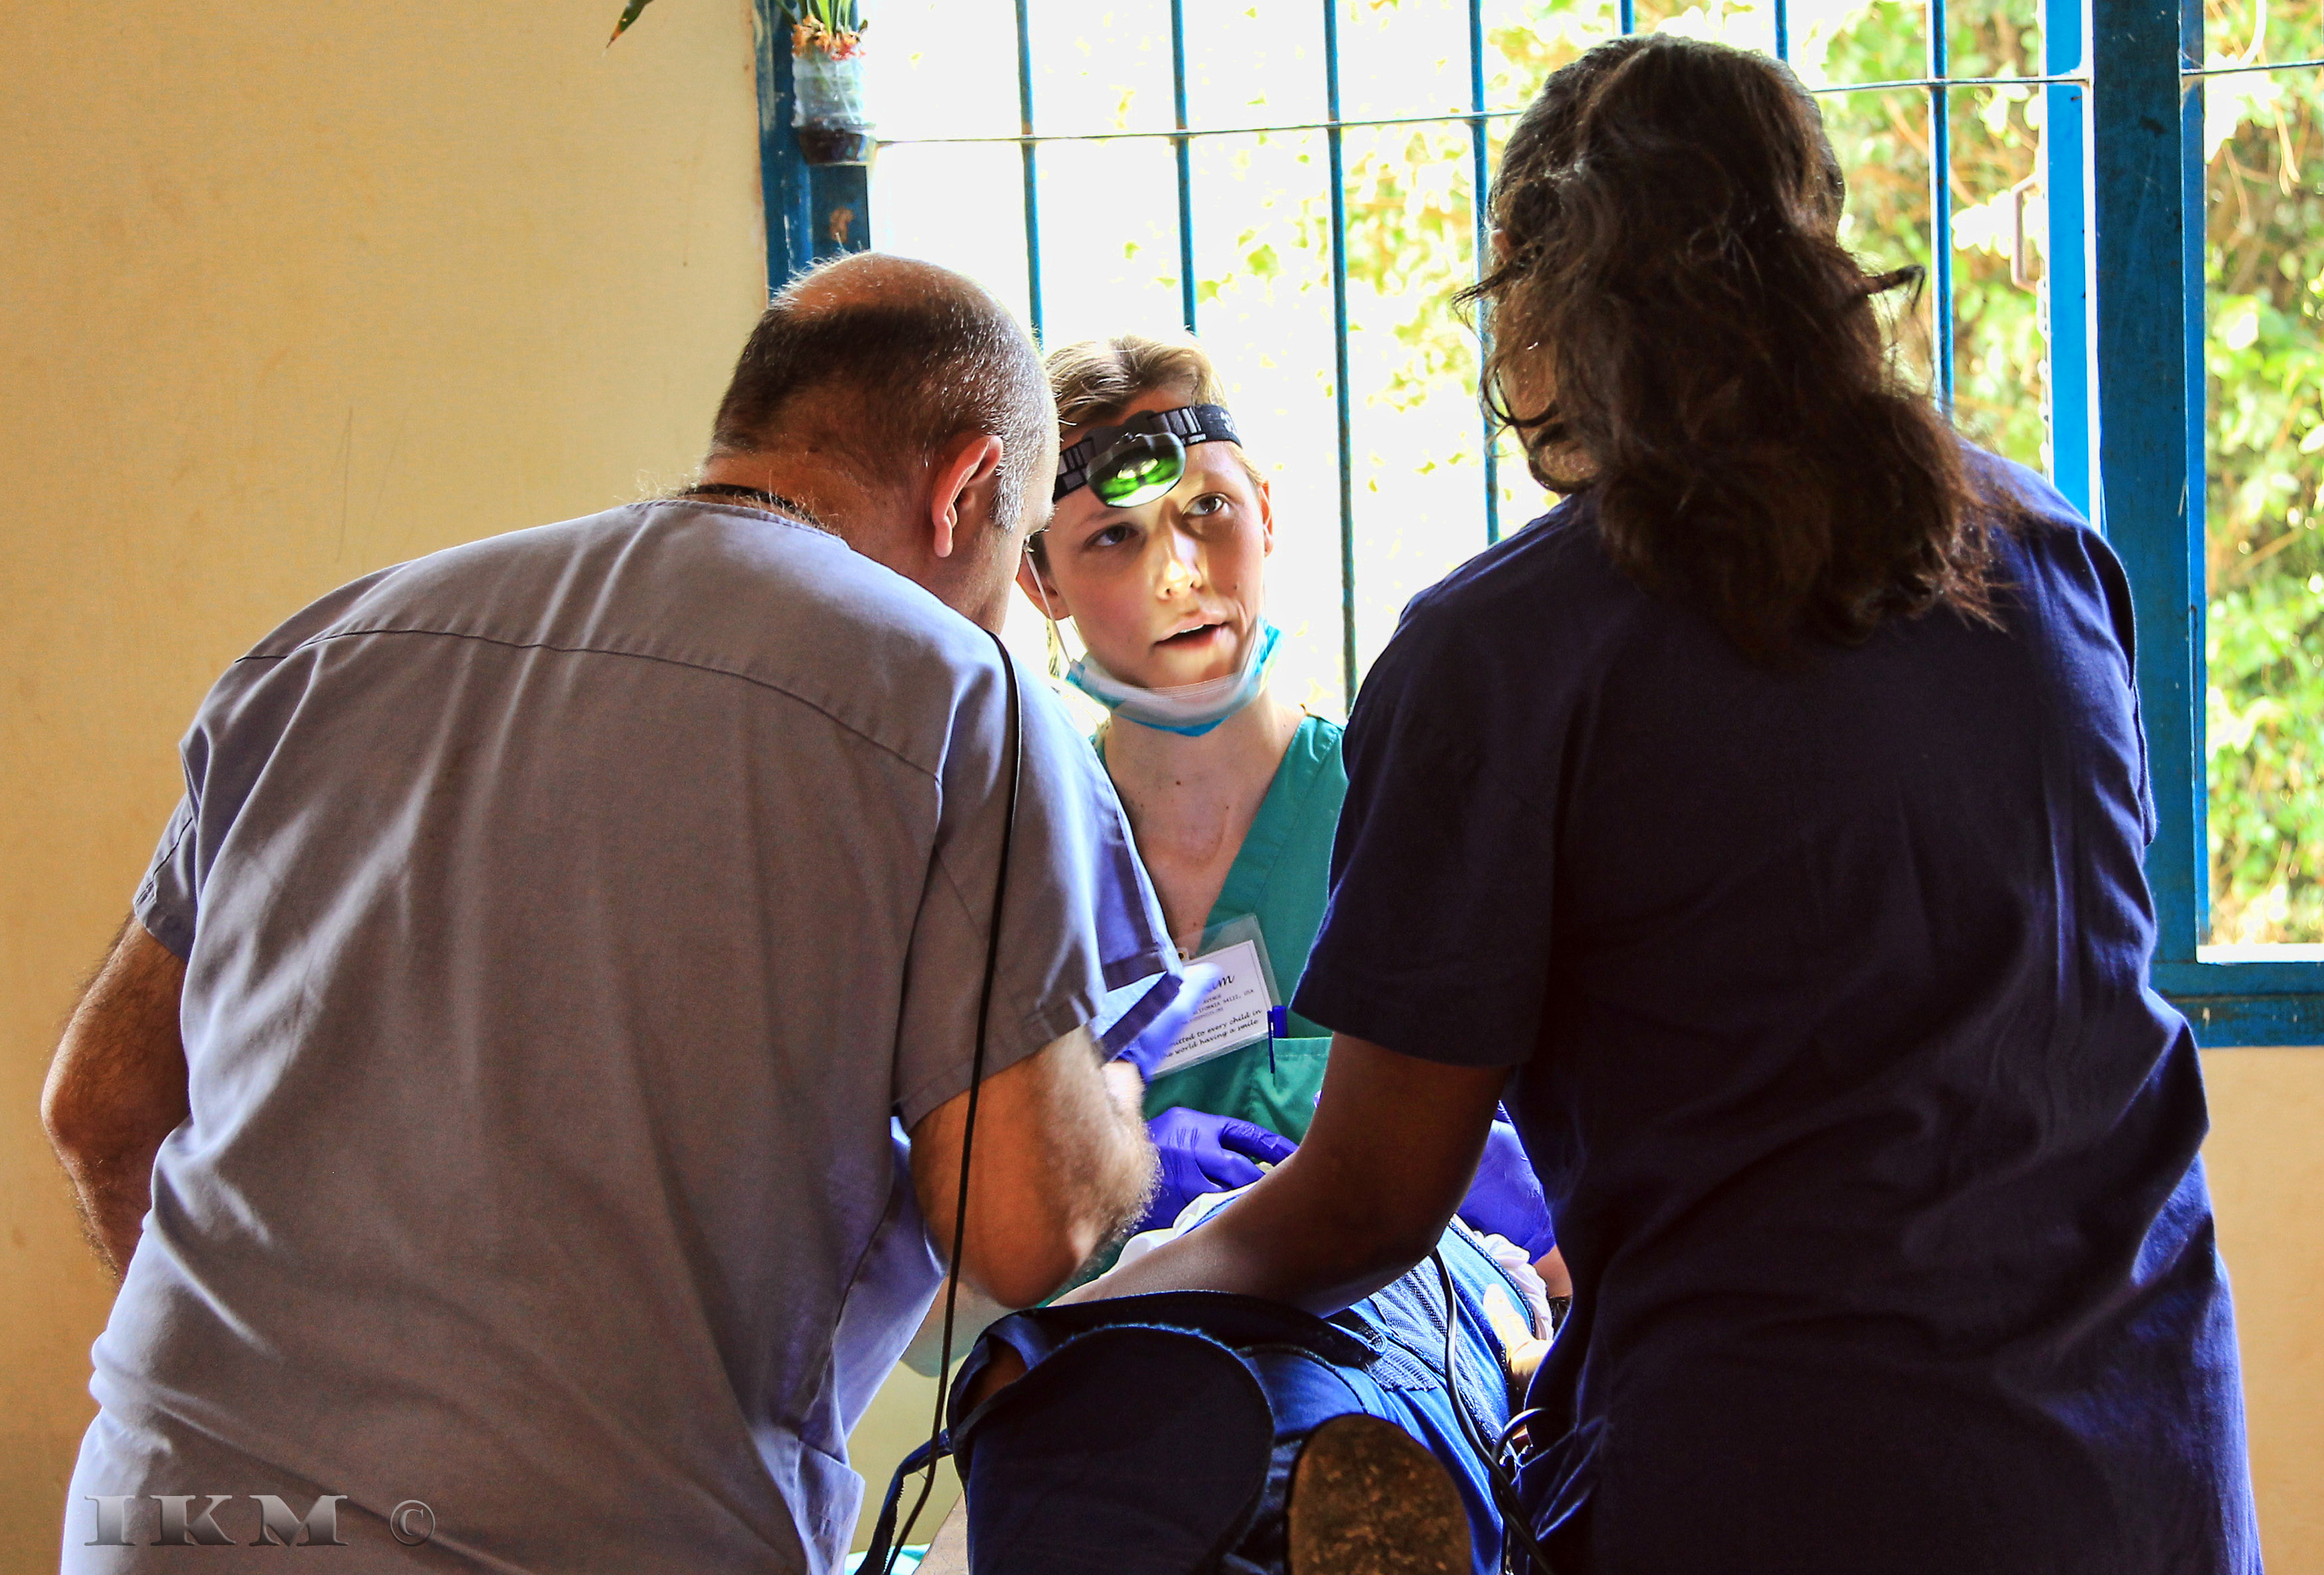
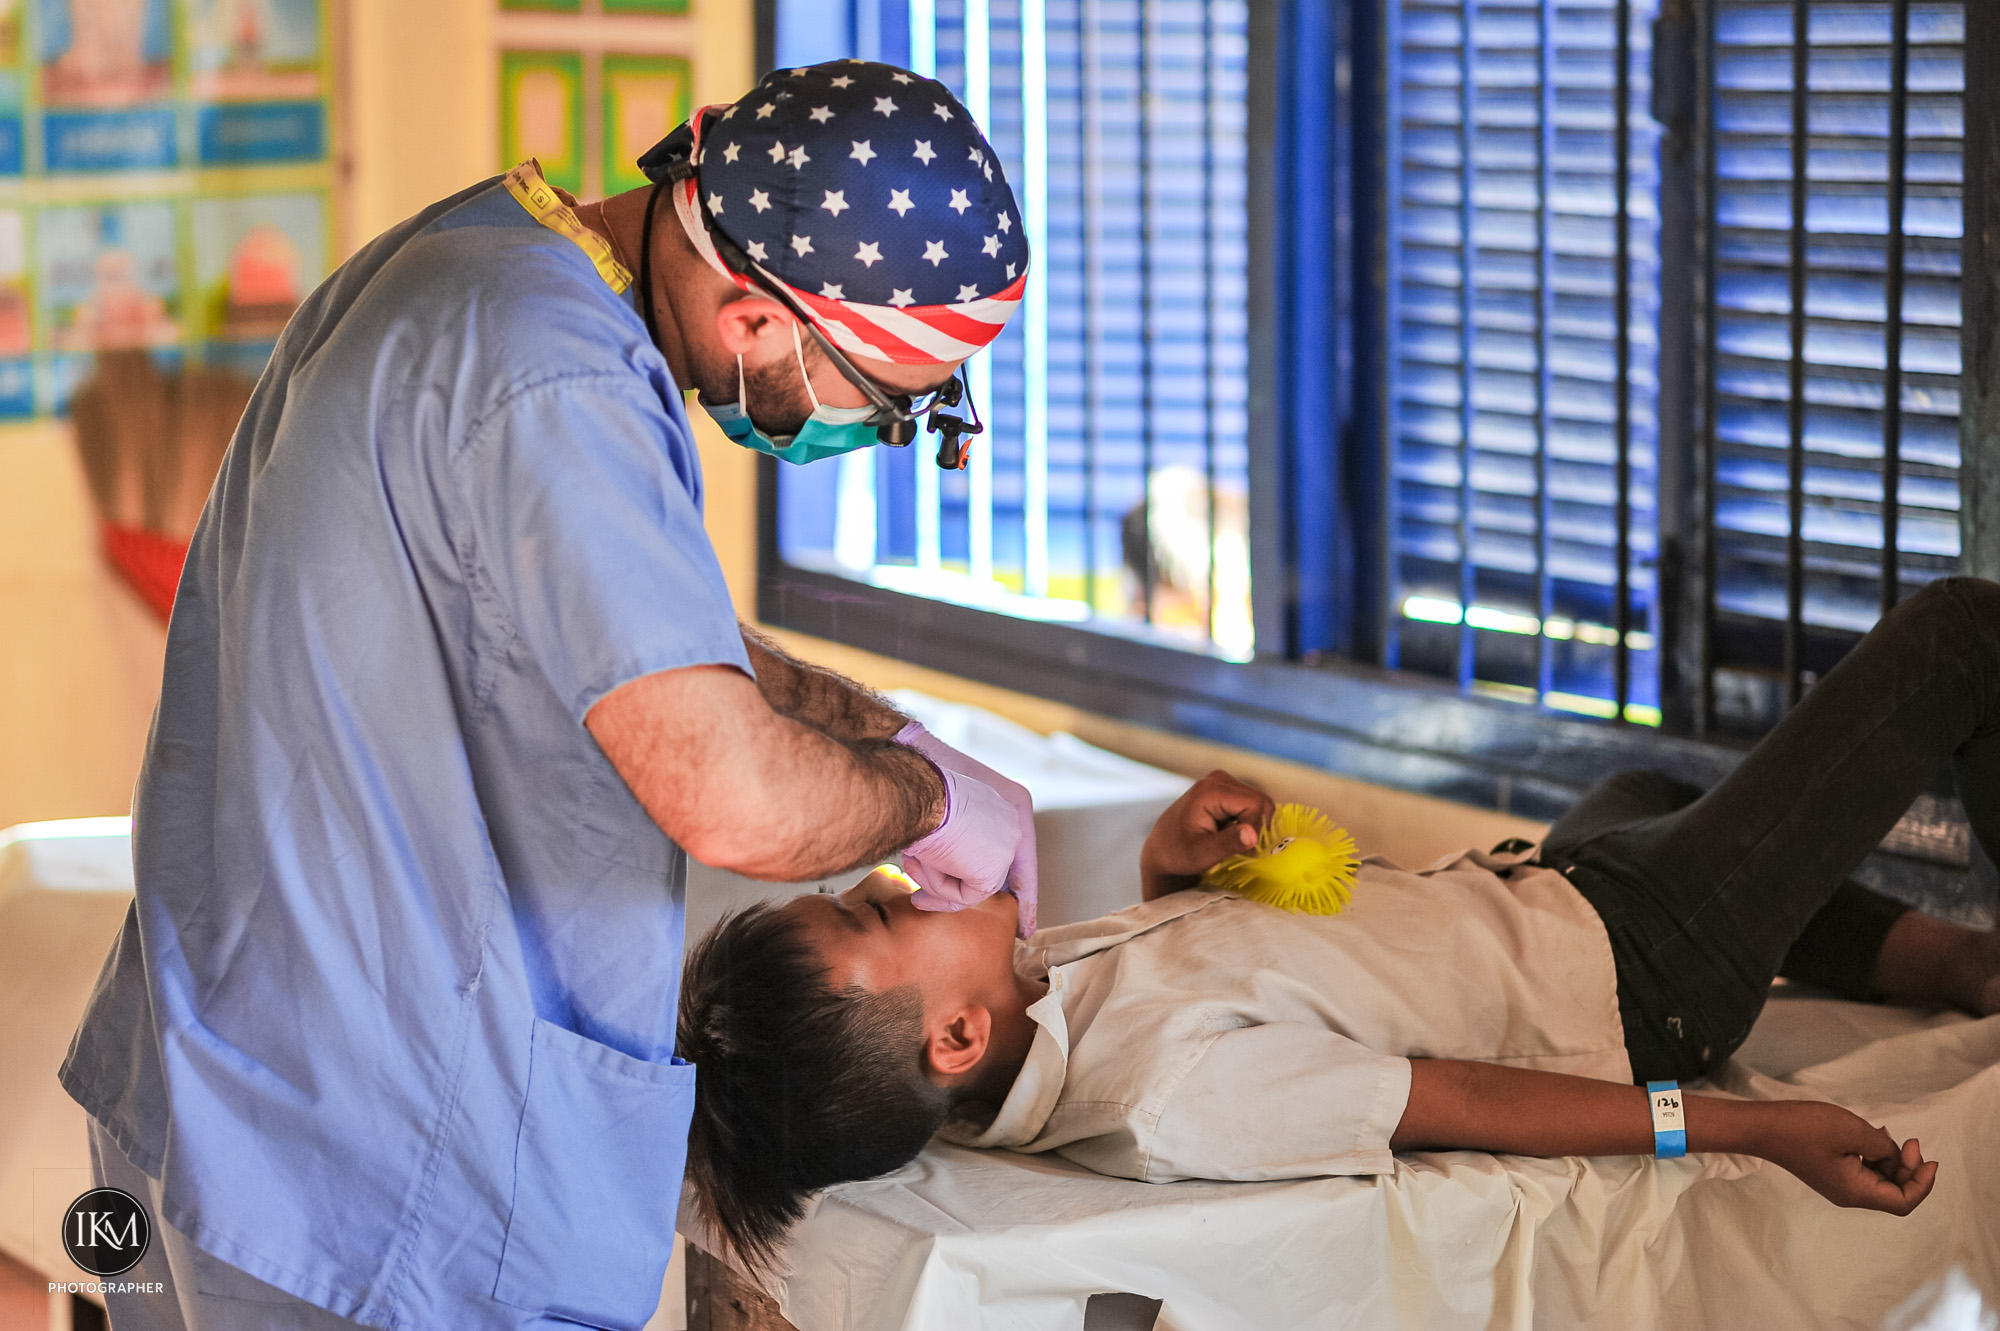
A child lying on a temporary treatment table, a dentist concentrating beneath a headlamp, classmates watching through a window: these are some of the scenes in my photographs of Kids International Dental Services in Cambodia. They show skilled work taking place in buildings borrowed for another purpose. They also show how many people are needed around the person holding the instruments.
My contribution was photography. I could record the concentration, the waiting, the organisation and the exchanges around the treatment. Those pictures belong alongside the organisation’s history because they show what its purpose looks like when people put it into practice.

The team gathered behind the KIDS Dental Mission Cambodia banner. Photograph: Ian Kydd Miller.
Kids International Dental Services, usually known as KIDS, is a United States nonprofit providing free dental care to children in communities with limited access to treatment. Based in San Francisco, it identifies itself as a 501(c)(3) charitable organisation, with EIN 94-3477276. Its purpose also includes encouraging young dental professionals to make volunteering part of their careers. 1
The strongest institutional account identifies Dr Robert P. “Bob” Renner as its founder. Stony Brook University’s School of Dental Medicine dates the founding to 2009 and identifies Renner as a retired faculty member. An outreach listing describes him as a retired prosthodontist and professor emeritus whose overseas volunteering preceded the organisation. He brought a long professional background to a setting where dentistry often had to be delivered with portable equipment and limited facilities. 2
KIDS’ own history gives the beginning a collective character. A group of dental and non-dental volunteers returned from a mission in 2009 and decided to establish an organisation that would enable others to participate. They wanted to improve children’s access to care while introducing younger practitioners to service. Cambodia, Guatemala and the Philippines were the initial countries in that account. 3
There is a discrepancy in the founding dates. A 2015 profile of Renner in the Theta Chi magazine, The Rattle, gives 2007. KIDS and Stony Brook give 2009, while public records show US tax exemption issued in July 2009. The earlier date may refer to preceding activity, but the available material does not resolve the difference. The safest historical account uses 2009 as the principal organisational milestone and acknowledges that the work had earlier roots. 4
Dr Purobi Phillips, also identified as Purobi Phillips-Renner, was central to that development. Contemporary reporting names her as KIDS’ president; the 2015 profile describes her as president and chief executive. The university source explicitly names Robert as founder, but Purobi’s documented leadership makes clear that she was a leading organiser in her own right. 4
A Columbia University report provides an early view of their partnership. In spring 2009, Robert and Purobi invited four dental students—Rajesh Ameen, Gabriella Furdui-Carr, Kourtney Logan and Barnali Roy—to join a Cambodian mission. The report describes work near Phnom Penh’s rubbish dump and the demands placed on the students. It also records Purobi’s appreciation of their effort. Mentoring was already embedded in the undertaking. 6
That report describes examinations, oral-health instruction, fluoride treatment and toothbrush distribution. When time allowed, volunteers placed sealants on permanent molars; they also removed infected teeth and performed other necessary surgical treatment. It reported that a one- or two-week mission could see between 1,000 and 1,700 children. These figures describe the programme at that time, rather than a fixed capacity for every trip. 6
Understanding the programme requires distinguishing immediate treatment from prevention. Examination establishes what a child needs. Restorative work can preserve a tooth where feasible; extraction may be necessary when a tooth cannot be retained. Preventive treatment and education address a different problem: what happens after the team leaves. The appropriate clinical decision belongs to a qualified practitioner, following assessment of the individual child.
KIDS expresses its wider goals through education, community cooperation, mentoring and returning. Its model depends on relationships with both communities and volunteers. That intention matters, although a stated commitment to repeat visits should be distinguished from evidence that every location receives them regularly. 7
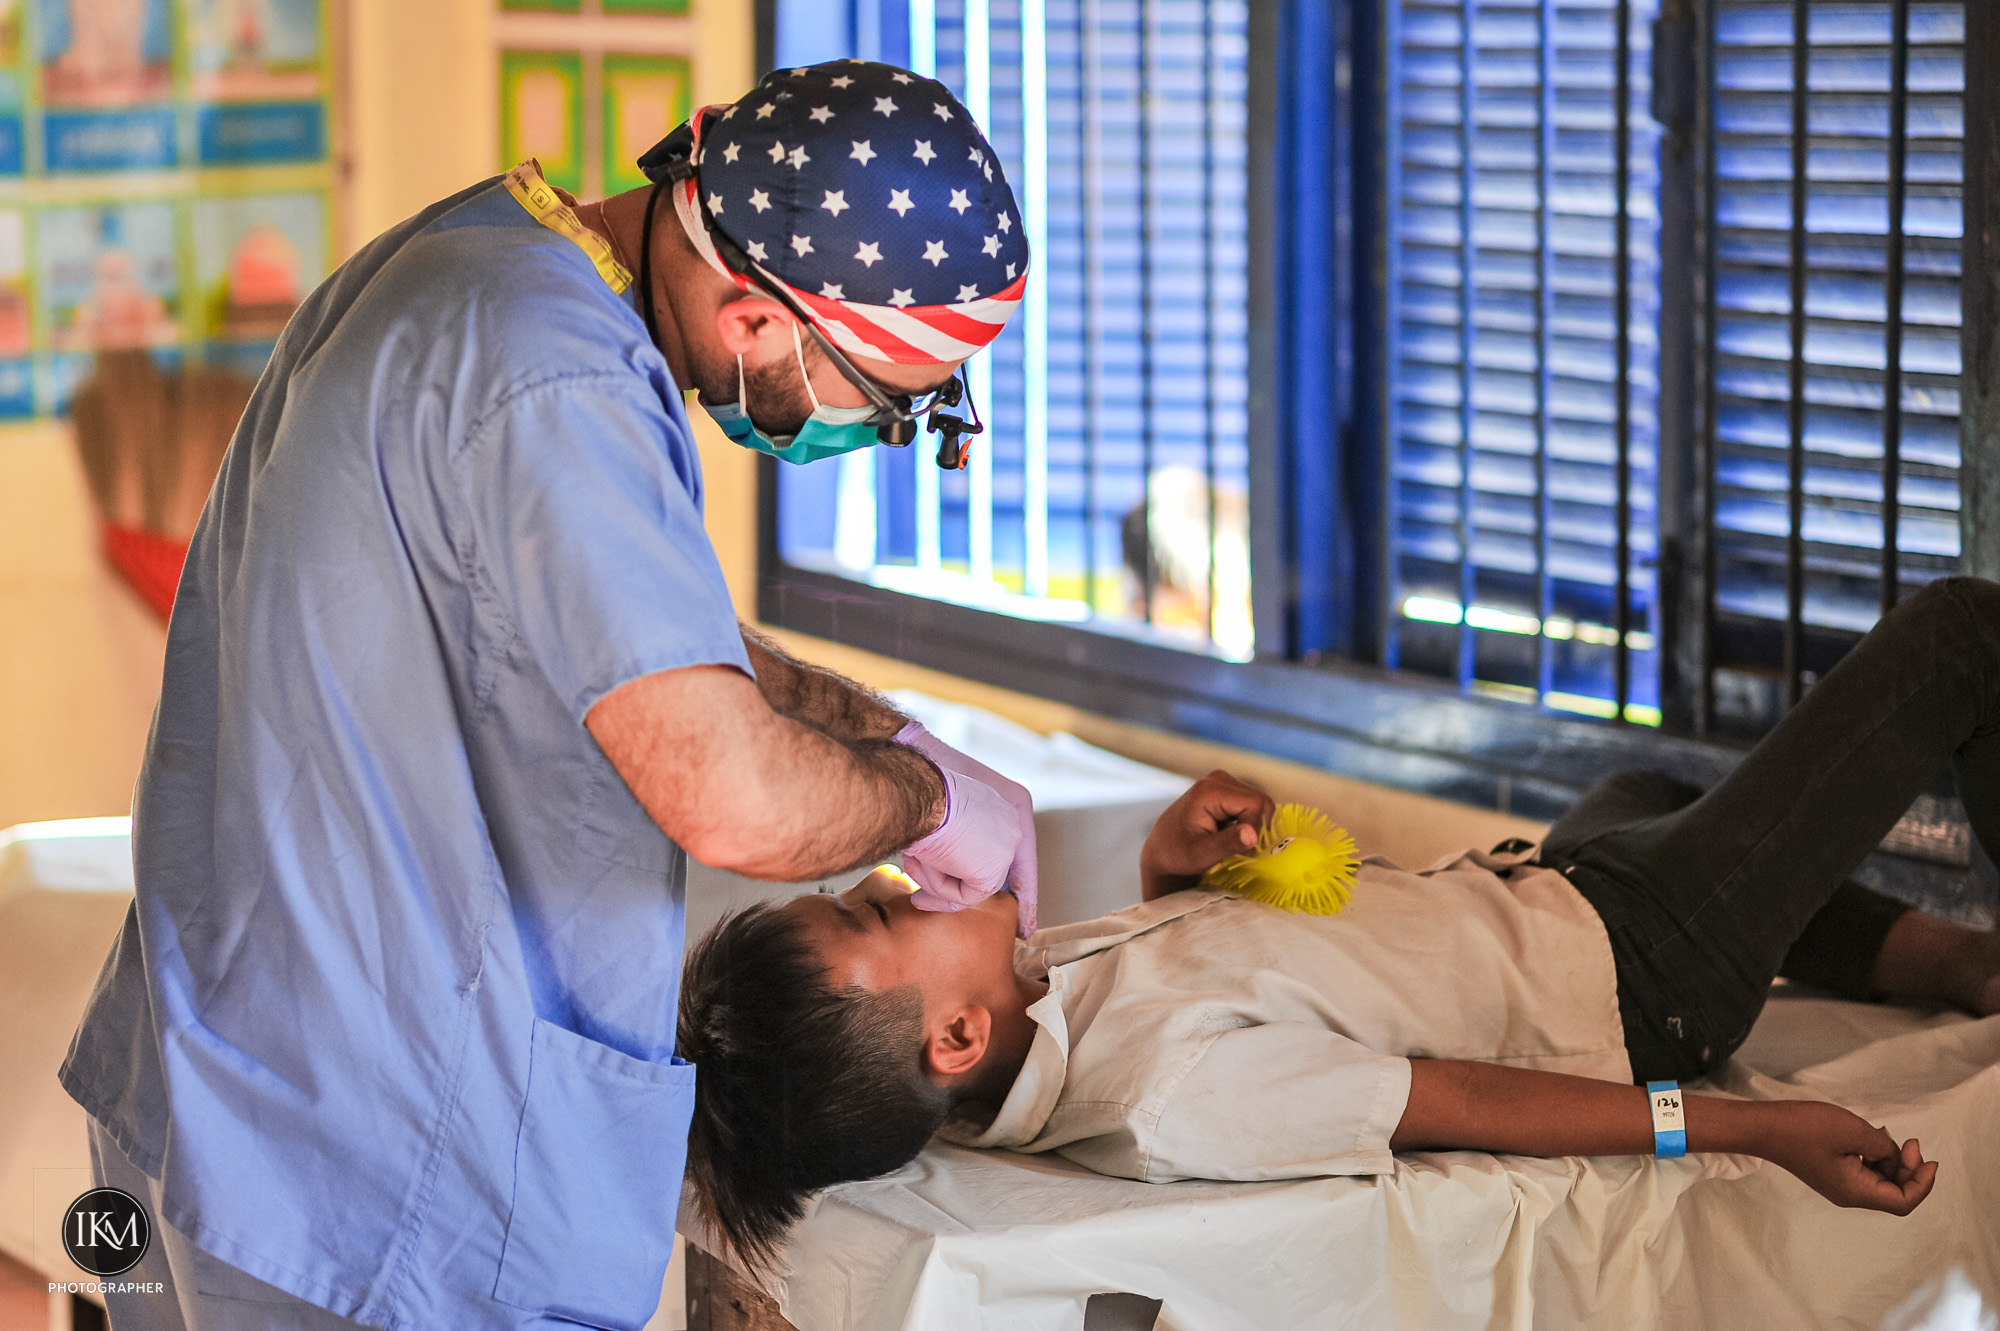
A temporary treatment station in Cambodia. Photograph: Ian Kydd Miller.

Cambodia became an important part of the organisation’s early work. Here, local partnerships provided access to children and places in which to operate. One documented partner was People Improvement Organization, or PIO, founded by Phymean Noun.
My reporting from 2010 recorded Bob Renner discussing treatment for PIO children over preceding years. He emphasised cooperation with local agencies and dentists, alongside educating children about daily dental care. That early account describes an international team and the practical limitations of delivering care away from a conventional surgery. 8
PIO’s own 2011 annual report independently confirms the relationship. One passage records services for more than 347 PIO students; another acknowledges dental diagnosis, fluoride treatment and extraction services for 600 children, credited to Bob Renner and Purobi Phillips of KIDS. The relationship between those figures is unclear, so they should not be added together. What the report establishes is a recognised contribution to PIO’s children’s services. 9
Contemporary reporting also documents outreach beyond those school connections. A March 2011 report attributed to Agence Kampuchea Presse described a two-week programme planned for Phnom Penh, Prey Veng, Svay Rieng and Kampong Cham. It identified treatment at Riverkids and the Tuol Sangke community and quoted Purobi describing a multinational group of dentists. Its anticipated reach of approximately 2,000 children was a target, not a verified final total. 5
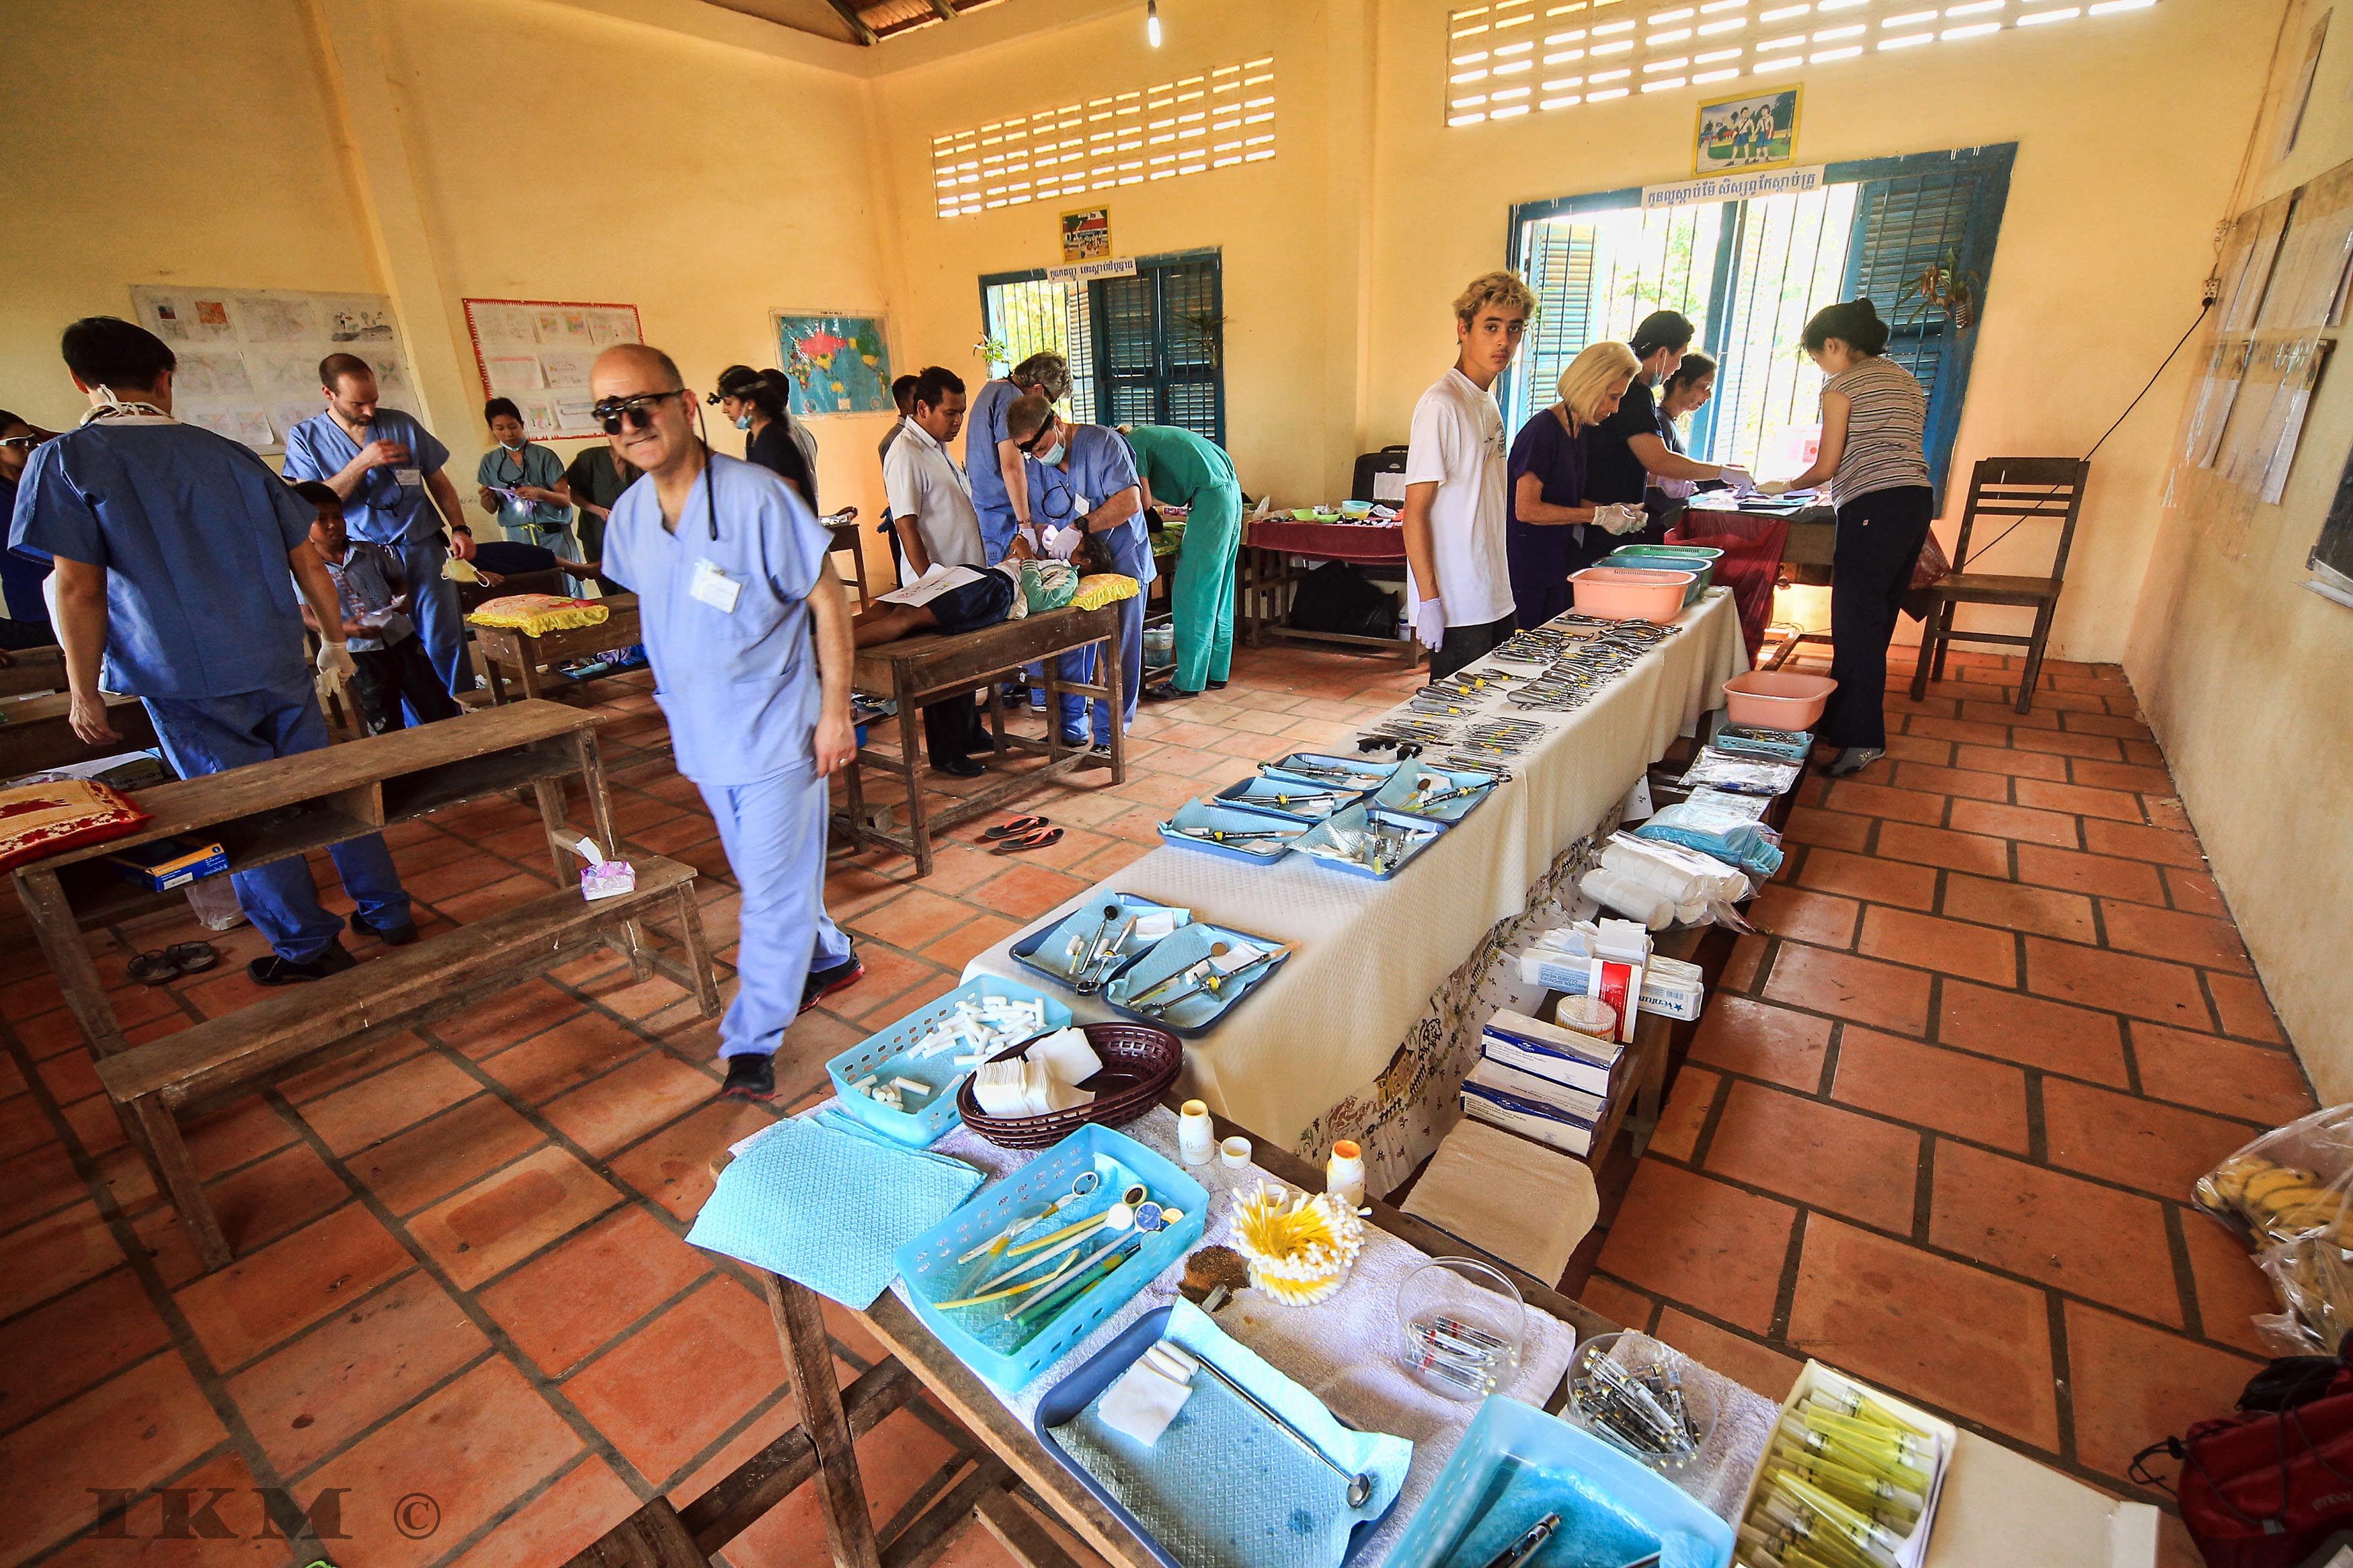
A more detailed account concerns the 2012 Cambodian mission involving Dr Jamie Diament-Golub, a paediatric dentist, and Dr Jon Golub, an orthodontist. They joined other dentists and support volunteers working in Phnom Penh and the countryside. At a Buddhist monastery in Prey Veng province, tables were adapted into treatment stations. The report described restorations, extractions and preventive care, with as many as 250 patients treated in a day. 10
The team also visited children at Cambodian Children Orphanage for Living and Training School—CCOLT—and PIO. Jamie reported that some children had received care through the programme over several years and described improvements in their oral health. This was a participating clinician’s observation, rather than a formal outcomes study, but it records the value attached to continuity. 10
My own January 2026 article, Why They Come, acknowledges David’s organisational contribution, the continuing work of Jon and Jamie, and the assistance of non-dental volunteers and local interpreters. David’s surname and formal position are not supplied in that account. Those contributions deserve recognition without inventing titles or completing identities from guesswork. 11

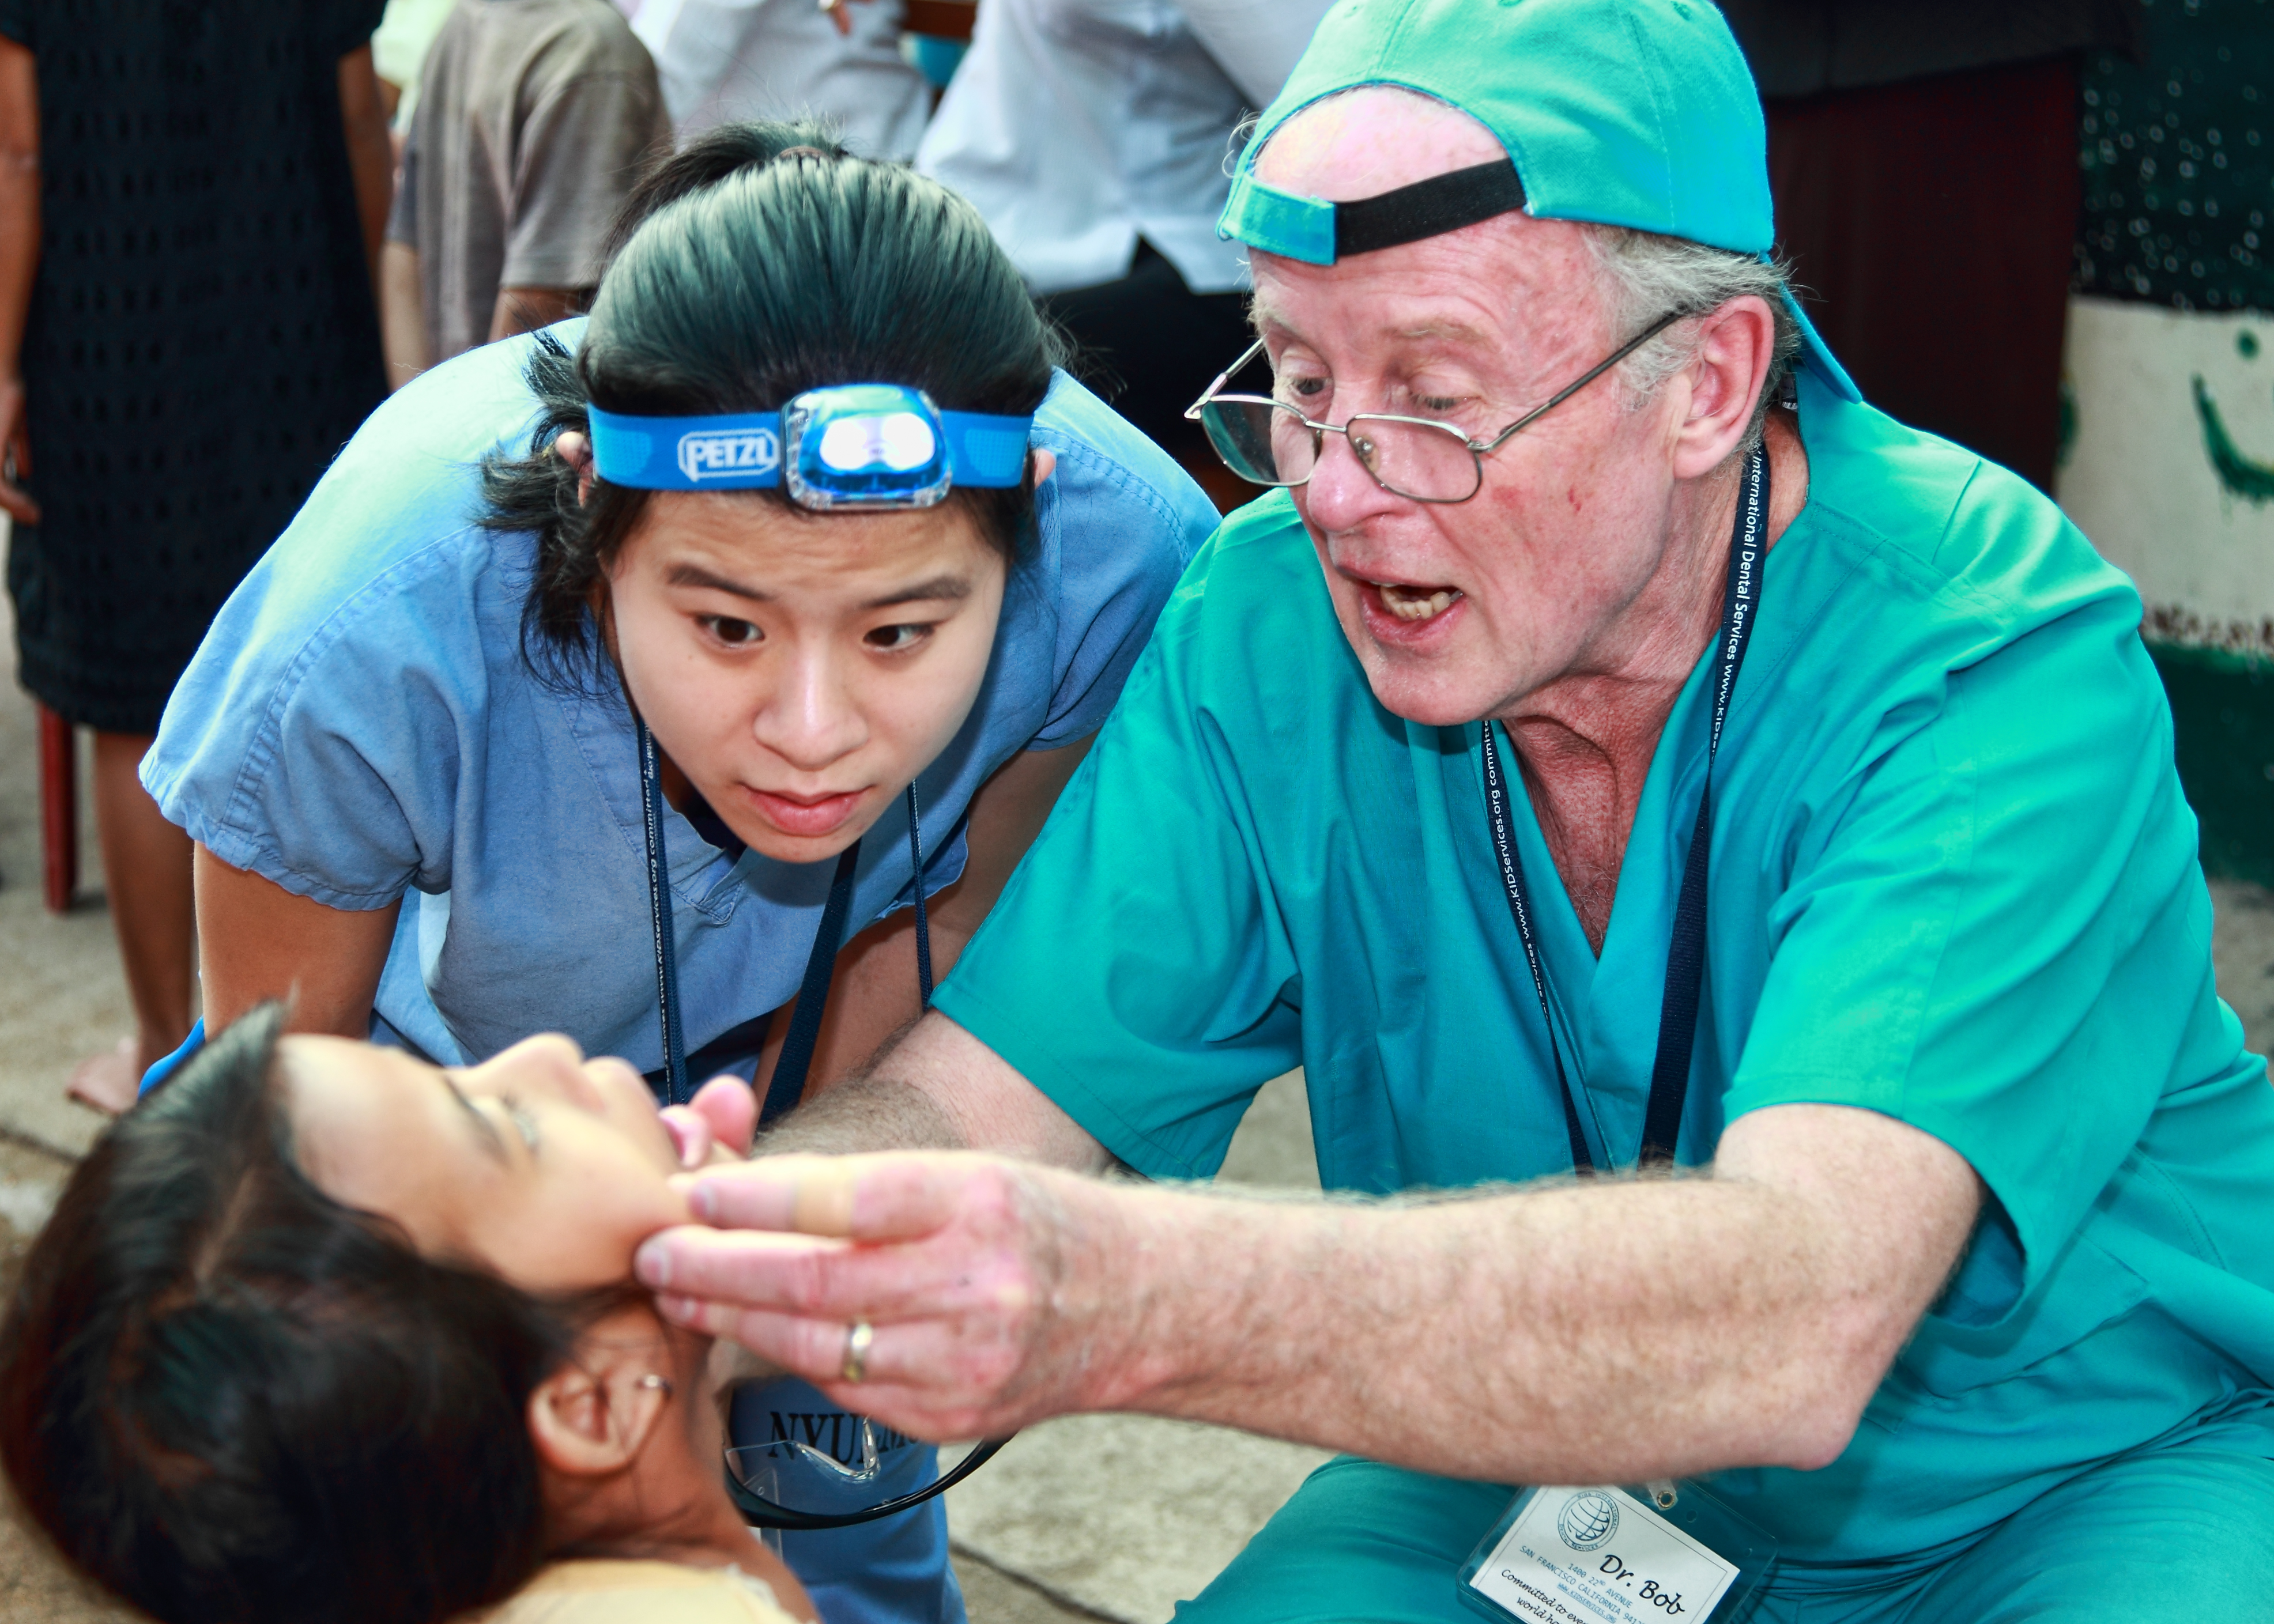
Conversation around a table during the Cambodian outreach work. Photograph: Ian Kydd Miller.
Another local partner account comes from Somnang Association. A post dated 16 December 2017 describes its annual appointment with KIDS dentists, working with Sreyka Smile Association, whose president it names as Stella-Désirée Bosch. It supplies no treatment totals, but adds evidence of an established local relationship. 12
The professional biography of Dr Marcus Yan, published by the Australian Dental Association’s New South Wales branch, records his involvement as a volunteer dentist and teacher with KIDS in Cambodia from 2014 to 2018. It separately lists work with the Cambodia Oral Health Partnership in February 2020. Those activities should retain their separate attribution. 13









Together, these accounts show a Cambodian programme involving several organisations, locations and groups of volunteers over time. They do not amount to a complete mission register. They do, however, give the history more substance than an undated statement that a charity “works in Cambodia”.
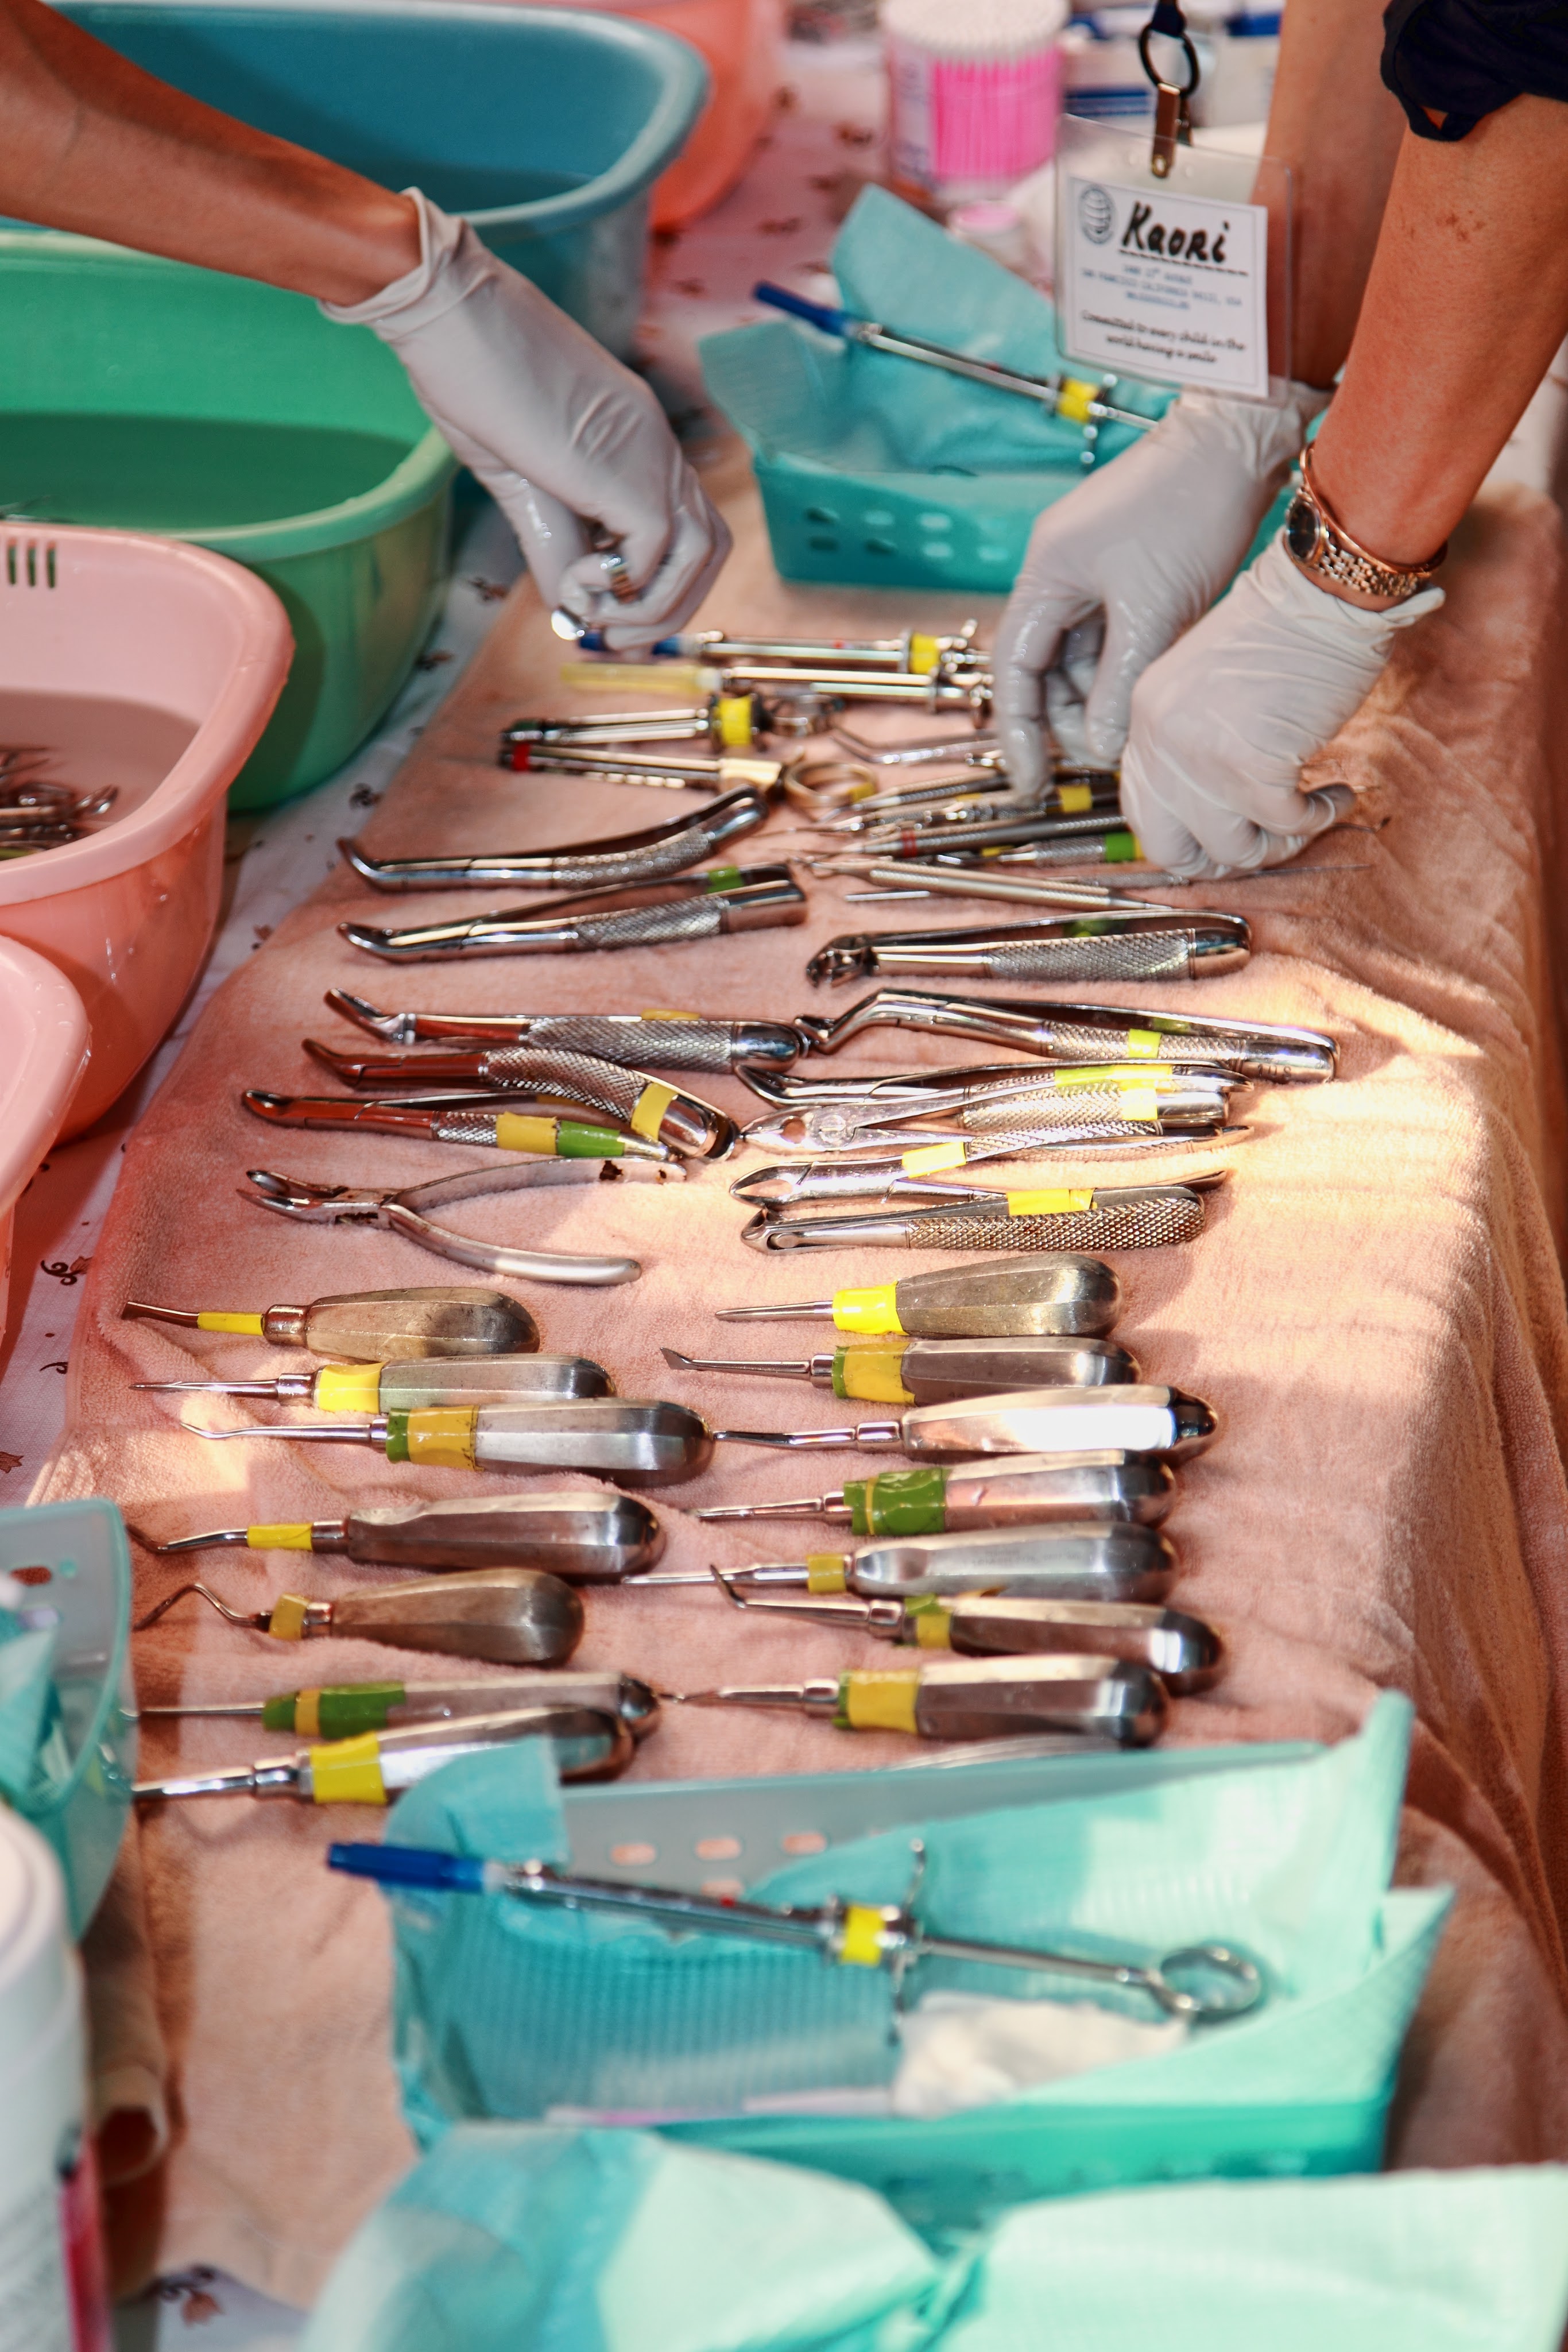
The practical organisation deserves attention. A temporary clinic requires a suitable space, equipment, supplies, clinical assessment, communication and a way to manage the children waiting. Translation helps families understand what is being proposed. Local teachers and organisers know the community in ways a visiting team cannot acquire in a few days.
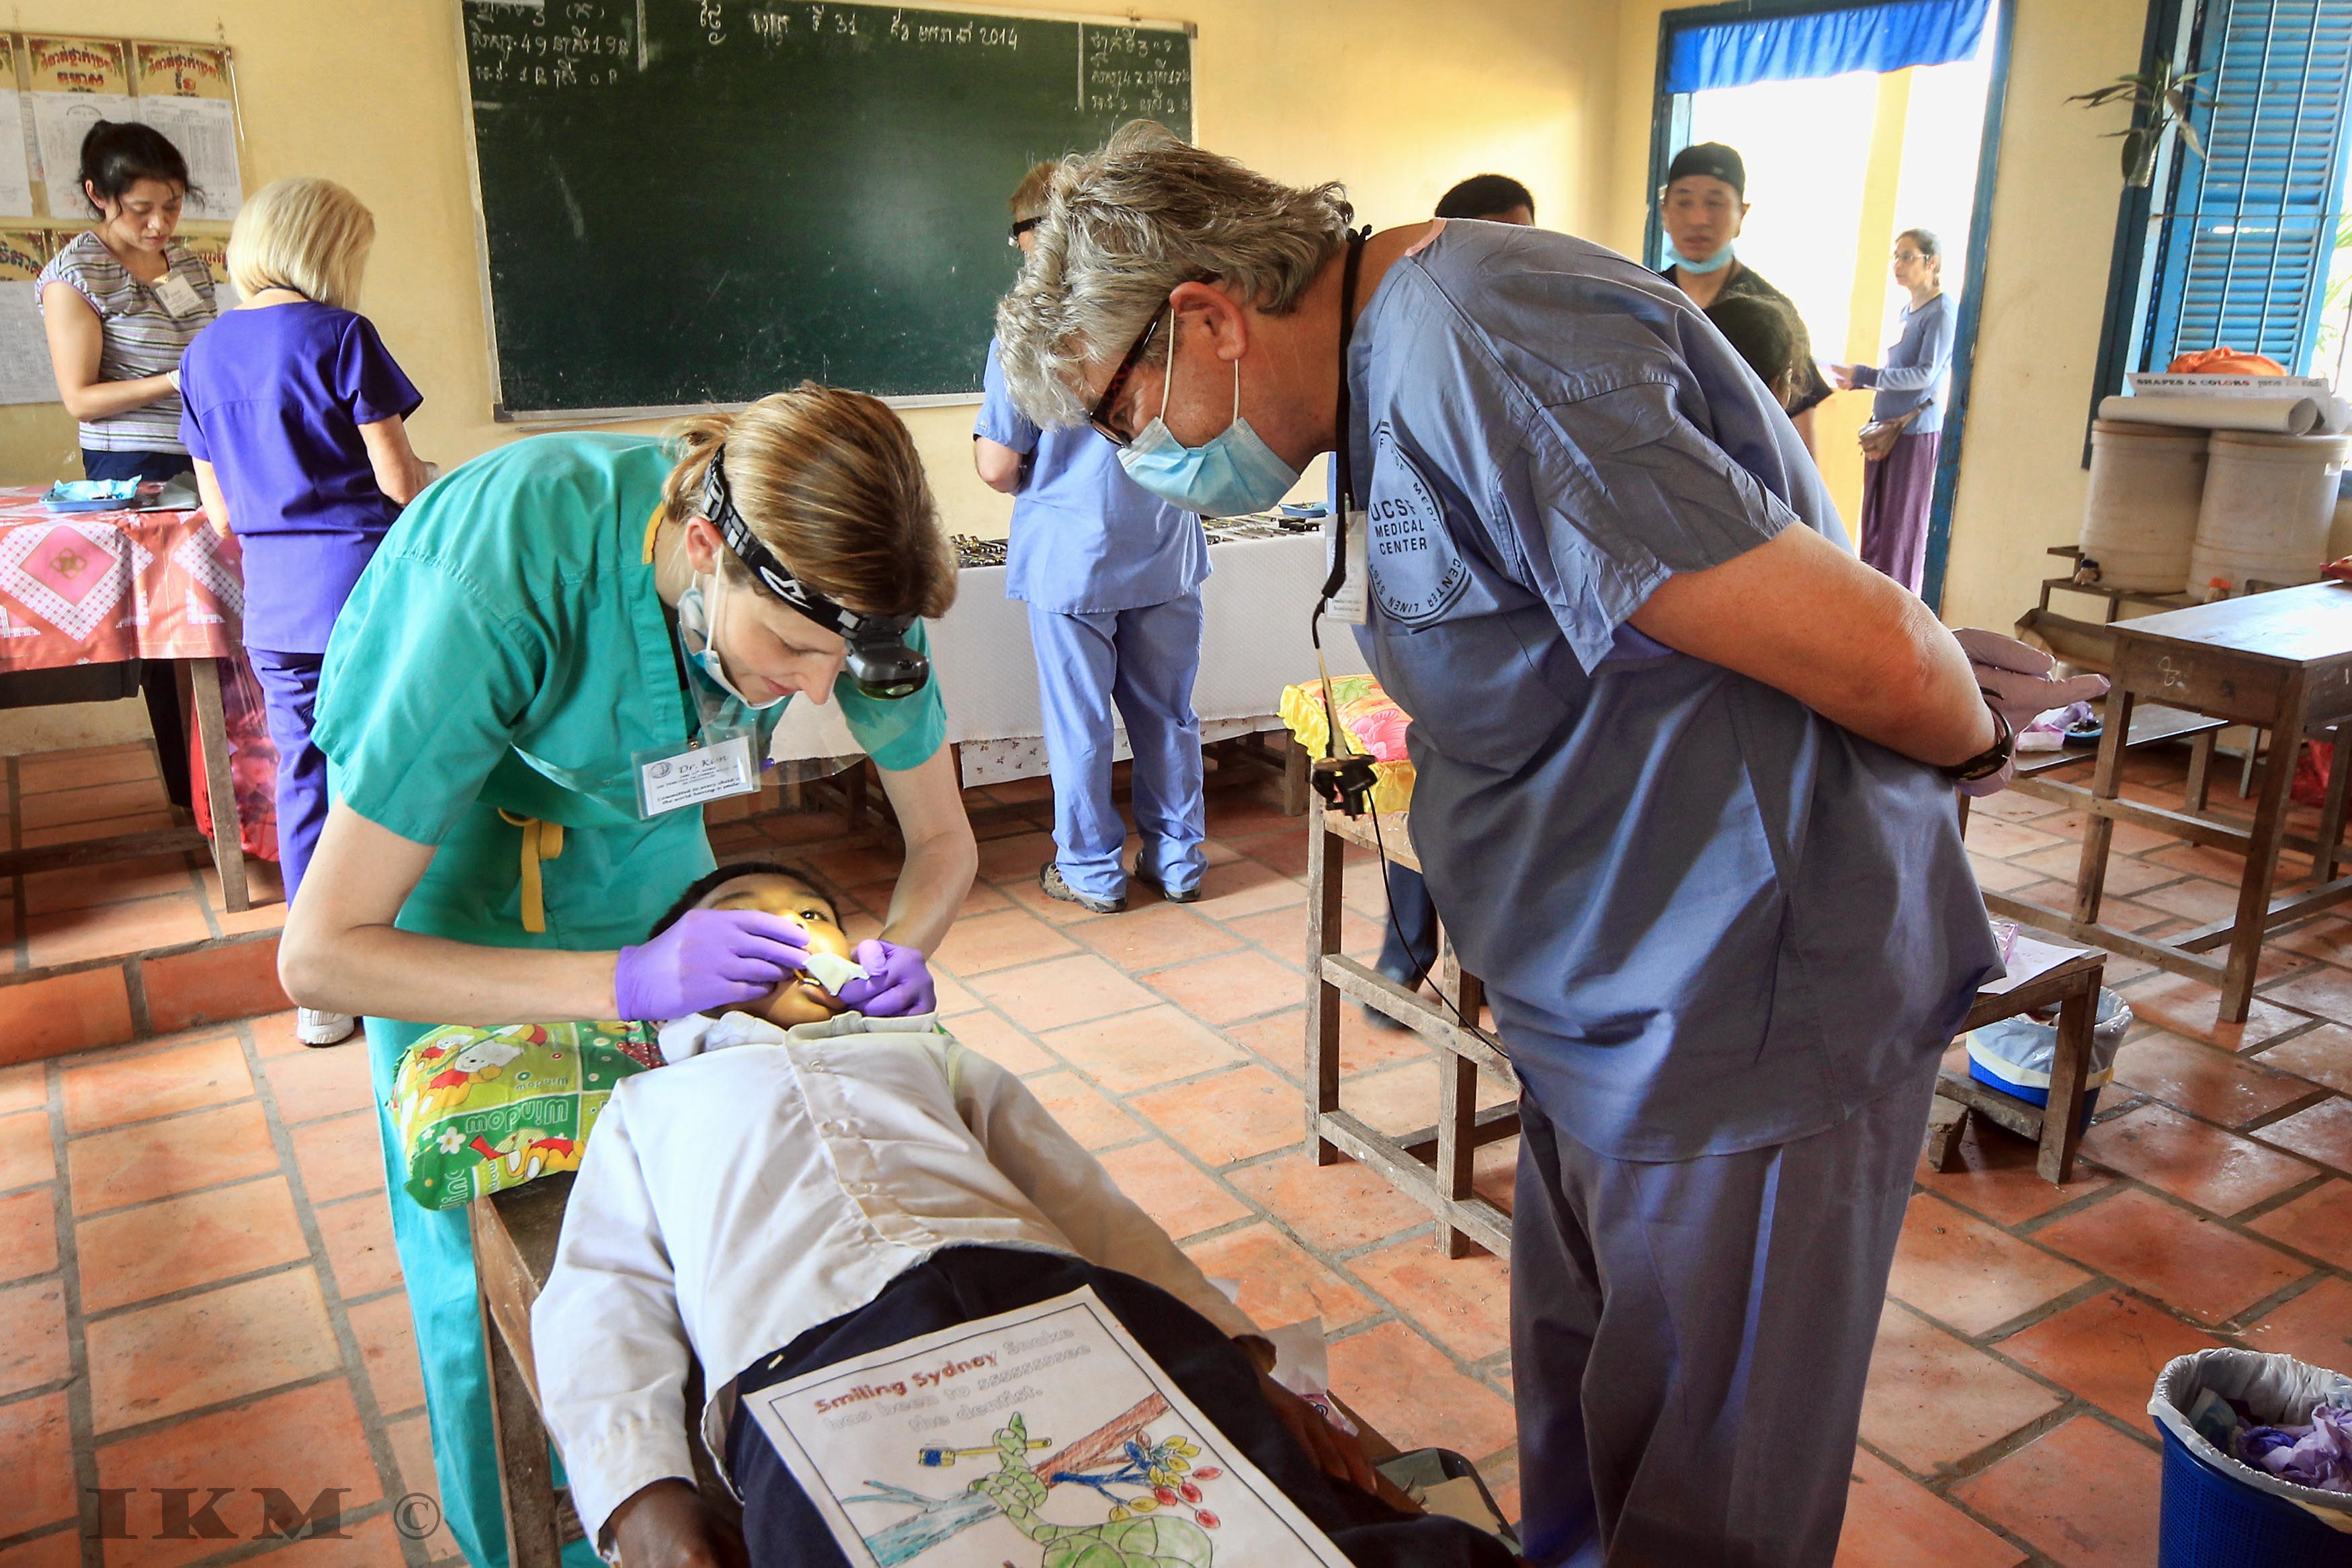






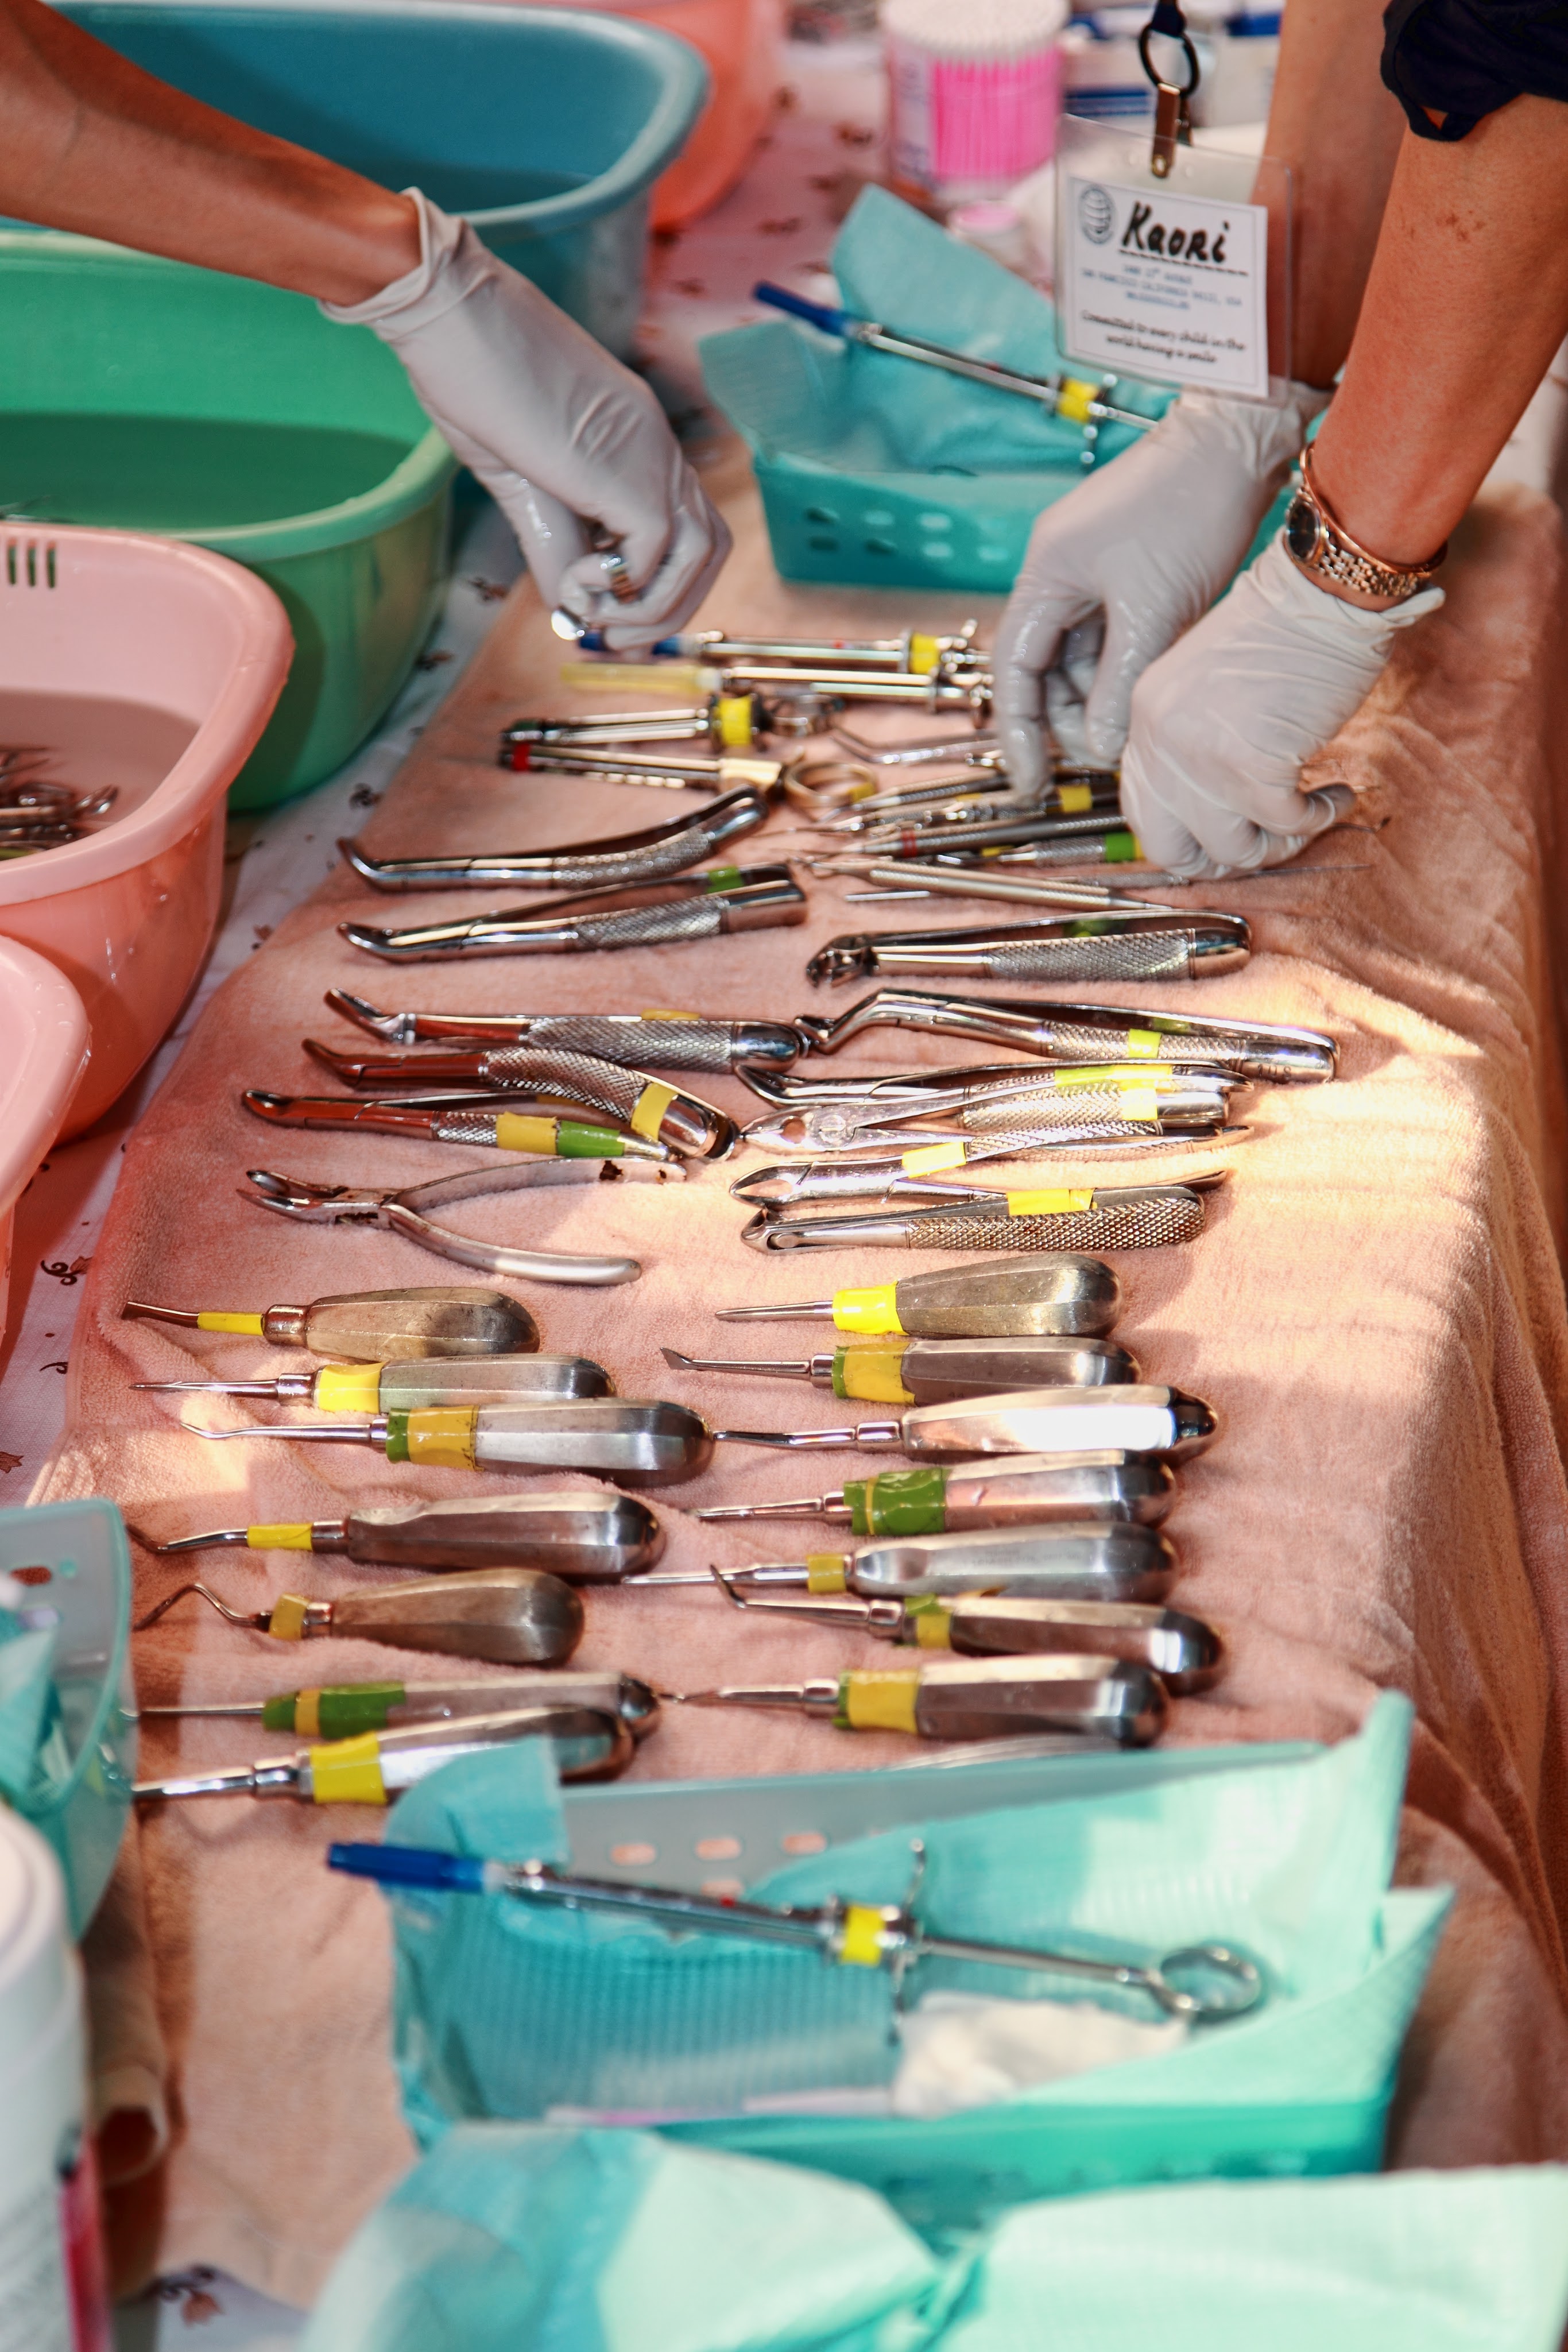


A school building and portable equipment can make treatment accessible. They also create obligations: infection prevention, appropriate consent, safe clinical practice, records and arrangements for problems that cannot be resolved during the visit. These are questions by which any outreach programme should be assessed. Photographs can show activity; they cannot independently certify every clinical process.

A volunteer attends to a girl’s fingernails while other pupils watch through the railings. Photograph: Ian Kydd Miller.
Some of the work happens outside the treatment station. In one of my photographs, a volunteer attends to a girl’s fingernails while other children watch. My account describes reassurance, interpretation and small gestures of attention around the dentistry. Such moments help explain why care cannot be measured solely by counting procedures. 14
The international programme grew beyond its original destinations. KIDS’ official history lists Cambodia, the Philippines, Guatemala, Cape Verde, Haiti, South Africa, Mongolia and Morocco. This is a historical footprint, not proof that eight programmes operate continuously. 3
Reports from particular missions provide a clearer sense of scale. The 2015 Renner profile attributed to KIDS’ leadership a total of 8,085 children treated in 2014, with 5,161 teeth extracted and 572 restored, across Cambodia, the Philippines, Mongolia and Guatemala. These are reported organisational figures, not an independently audited lifetime total. 4
Stony Brook’s account of a 2019 Guatemala mission records 1,760 children receiving care in Nebaj and Chajul. Students Daniel Bastardi, Ethan Santore and Linda Zheng worked alongside experienced practitioners and other volunteers. Treatment included extractions, fillings, fluoride therapy and education. The report illustrates the connection between service and supervised professional learning. 2
Dr Reza Khazaie, of Willow Pass Dental Care in California, has documented participation in several KIDS missions. His practice reports 2,624 children seen during six days in South Africa in November 2017, and more than 1,900 children treated during a Morocco mission in 2023. These are participant-reported results. Its archive also contains a Cambodia heading followed by text about Haiti, so those particular figures cannot reliably be attributed to Cambodia. 15
Neither a large patient count nor a large extraction count tells the entire story. A count may describe examinations, preventive interventions or more extensive treatment. It may include repeat patients. Meaningful reporting distinguishes those categories and asks what follow-up was available. Volume helps describe activity; outcomes require further evidence.
The pandemic interrupted the programme. In March 2021, KIDS reported suspending international volunteer trips. It described working on fundraising, clinical systems, sterilisation procedures and support for communities in the United States, while planning future overseas visits. Cambodia was among the proposed destinations. 16
Its Facebook page subsequently supplied evidence of renewed activity elsewhere: a December 2022 update referred to work in Guatemala and Morocco, while a May 2024 post recruited volunteers for Nepal and included photographs described as being from the previous year. Those posts help document post-pandemic activity, but do not establish the dates of later Cambodian missions. 17
As of 15 November 2026, the public material reviewed does not provide a complete, dated register of recent Cambodia visits. The official volunteer page continues to list Cambodia in January and February without identifying a year. My articles published in 2026 contain extensive Cambodian photographs, but publication and upload dates alone do not establish when each picture was made. 18
The organisational record also requires a distinction between KIDS and the Phillips Renner Foundation. Robert Renner and Purobi Phillips established that separately named charity, which describes work in dental care, nutrition and education. It has a separate tax identity. The material reviewed does not establish that KIDS simply changed its name to the foundation. 19
A February 2026 announcement about Dr Wendy Liao’s Philippines outreach credits the Phillips Renner Foundation as organiser and names Bob and Purobi as leaders. It demonstrates their continuing humanitarian involvement, but its treatment figures should not be transferred into KIDS’ totals. 20
Public tax records provide another part of the picture. Earlier KIDS filings name Purobi Phillips as president. The latest return reviewed, for 2025, lists Dr Nate Geodias, Dr Justin Newberry and Kimberly Baer as president, chief financial officer and secretary respectively, all with zero reported compensation. Earlier filings spell the president’s surname Gerodias; later extracted records use Geodias. 21
| Financial year | Reported revenue | Reported expenses | Year-end net assets |
|---|---|---|---|
| 2023 | $12,044 | $13,775 | $291,860 |
| 2024 | $4,759 | $17,534 | $279,085 |
| 2025 | $1,134 | $22,052 | $258,167 |
Figures from the IRS-derived records published by ProPublica’s Nonprofit Explorer. 21
These accounts describe reported organisational finances, not necessarily the full value of donated time or spending borne directly by volunteers. They do not measure clinical outcomes. Equally, a charity’s statement that donations support its mission should be read alongside its accounts and programme reports rather than treated as a complete financial explanation.
KIDS invites enquiries about donating money or supplies and joining missions. Its published contact is replytokids@gmail.com, and its volunteer page requires signed documentation. Prospective volunteers should confirm the particular mission’s dates, clinical roles, supervision, local permissions, costs and follow-up arrangements. Donors can ask which programme a contribution will support and what reporting will follow. 18

A child beside a classroom doorway. Photograph: Ian Kydd Miller.
For me, photography belongs within that responsibility to explain. A picture should help people understand the work without humiliating the person receiving care. A child’s fear does not become public property because treatment is free. Clinical photographs require particular care in how they are made, selected, captioned and used.
My account of volunteering with a camera argues for showing cooperation and respecting the people in front of the lens. Local organisers and helpers belong in the record. So do the ordinary moments between procedures. The camera can preserve those relationships, but it cannot prove that every problem has been solved. 23









The evidence supports a history of experienced practitioners, younger professionals, students and general volunteers working with community organisations to deliver care that children might otherwise have struggled to obtain. It also leaves questions about complete rosters, recent mission dates, long-term outcomes and continuity. An honest history can acknowledge the work without filling those gaps with enthusiasm.











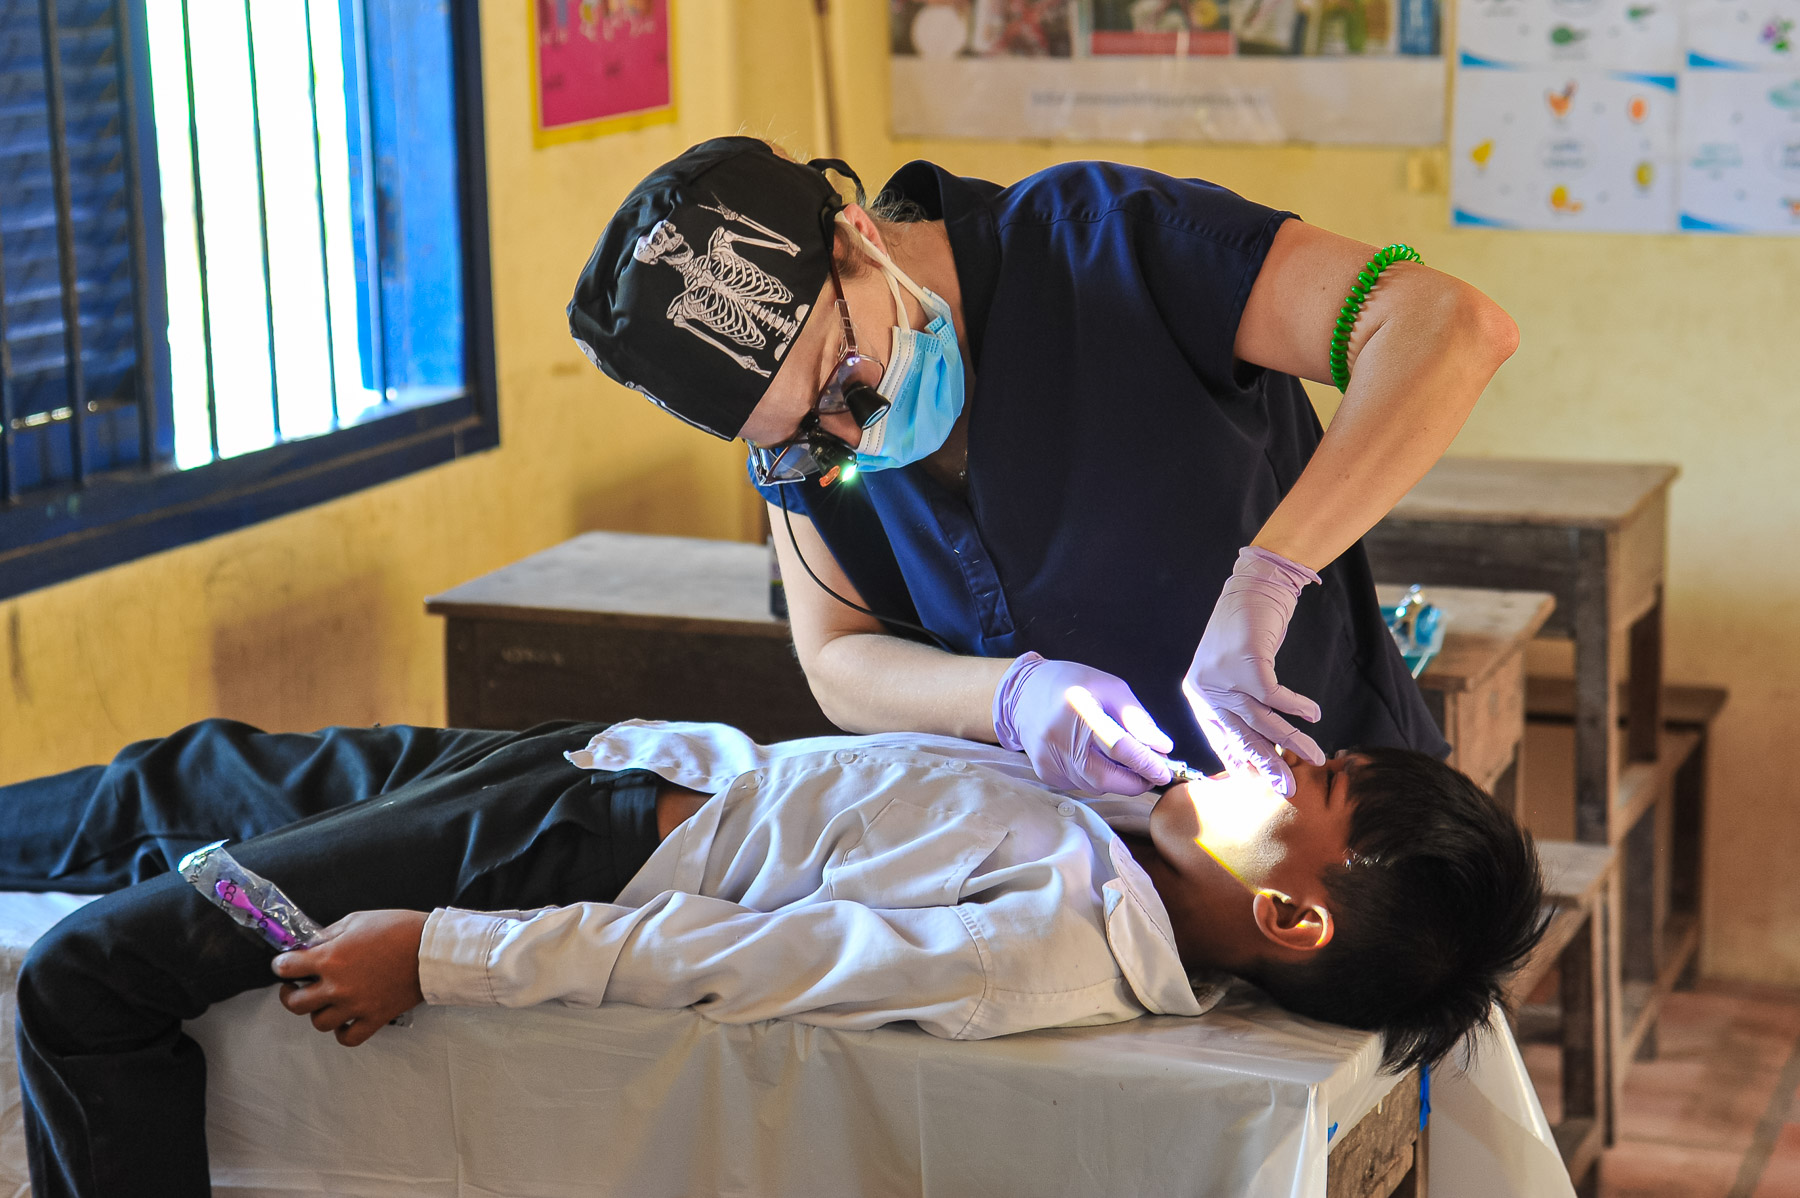







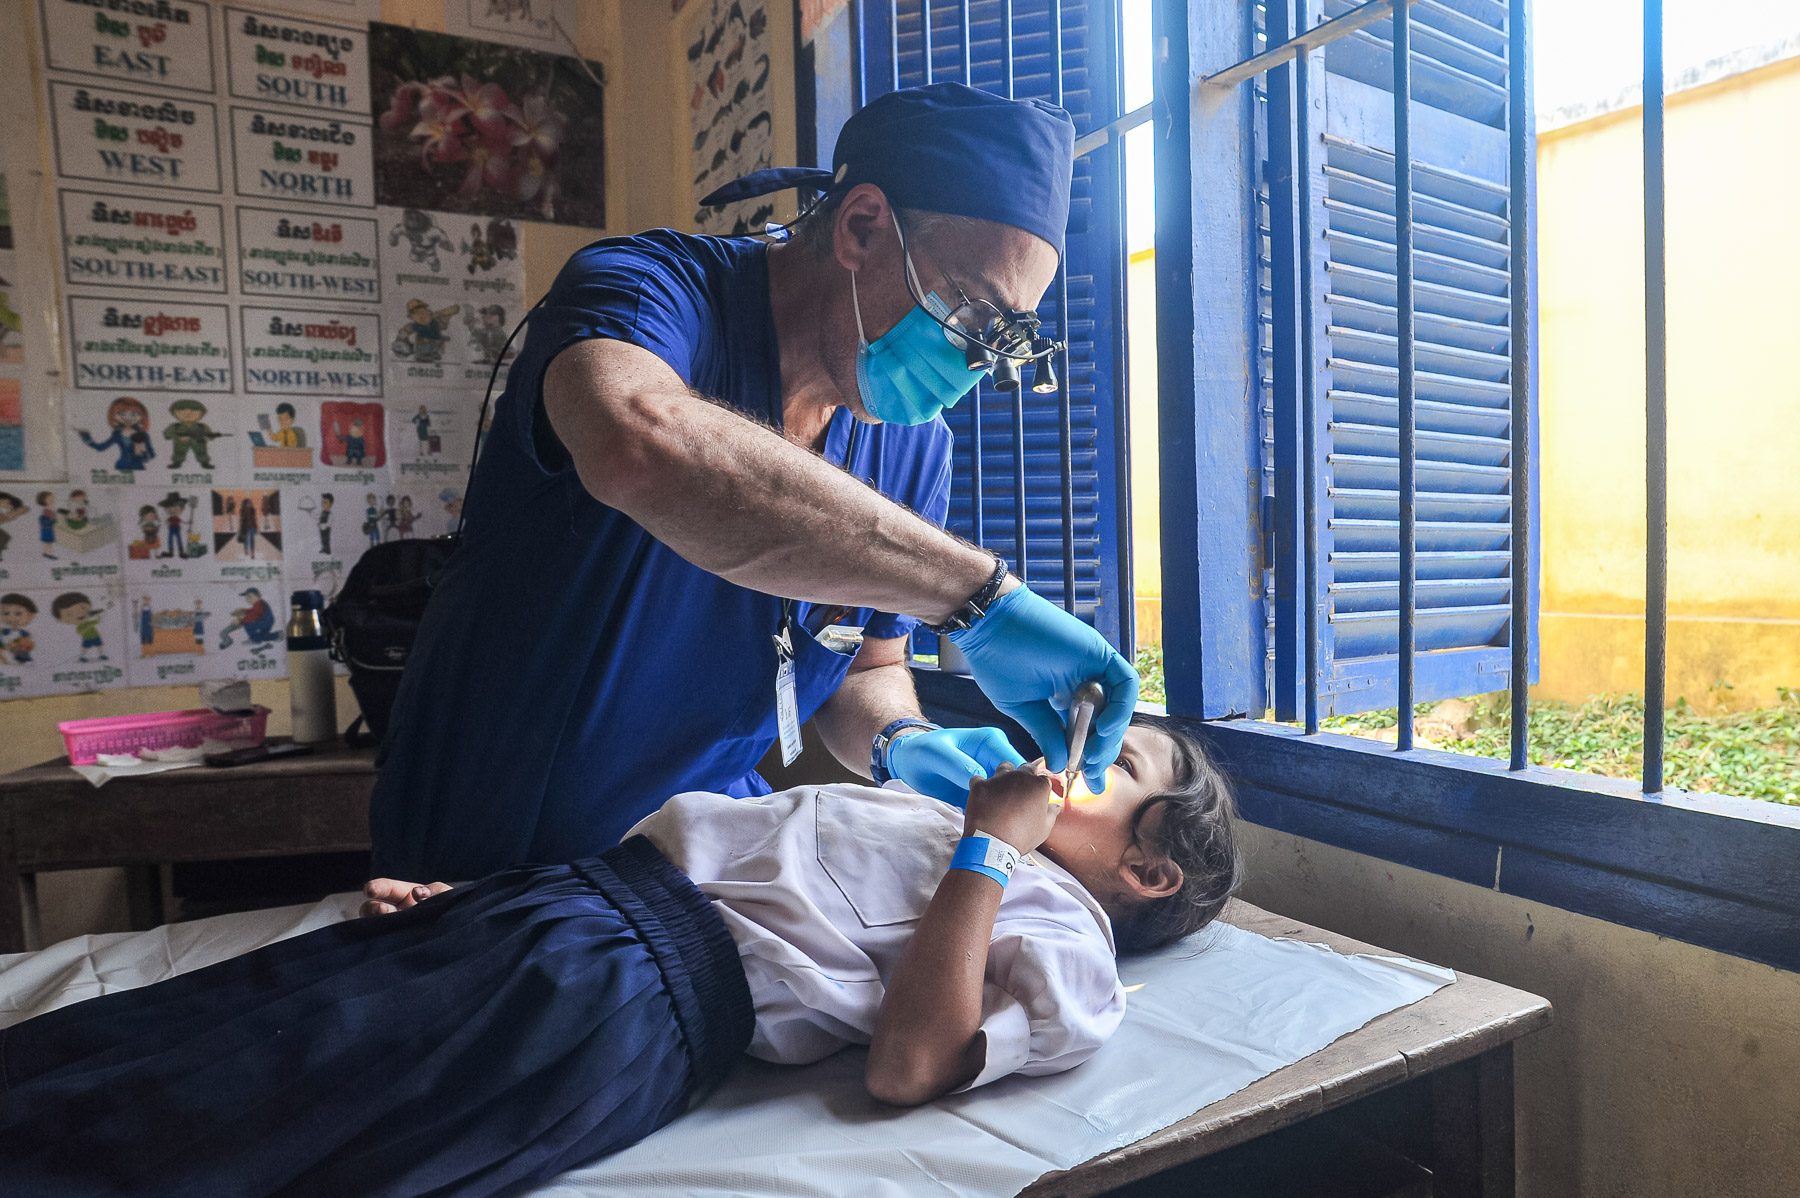




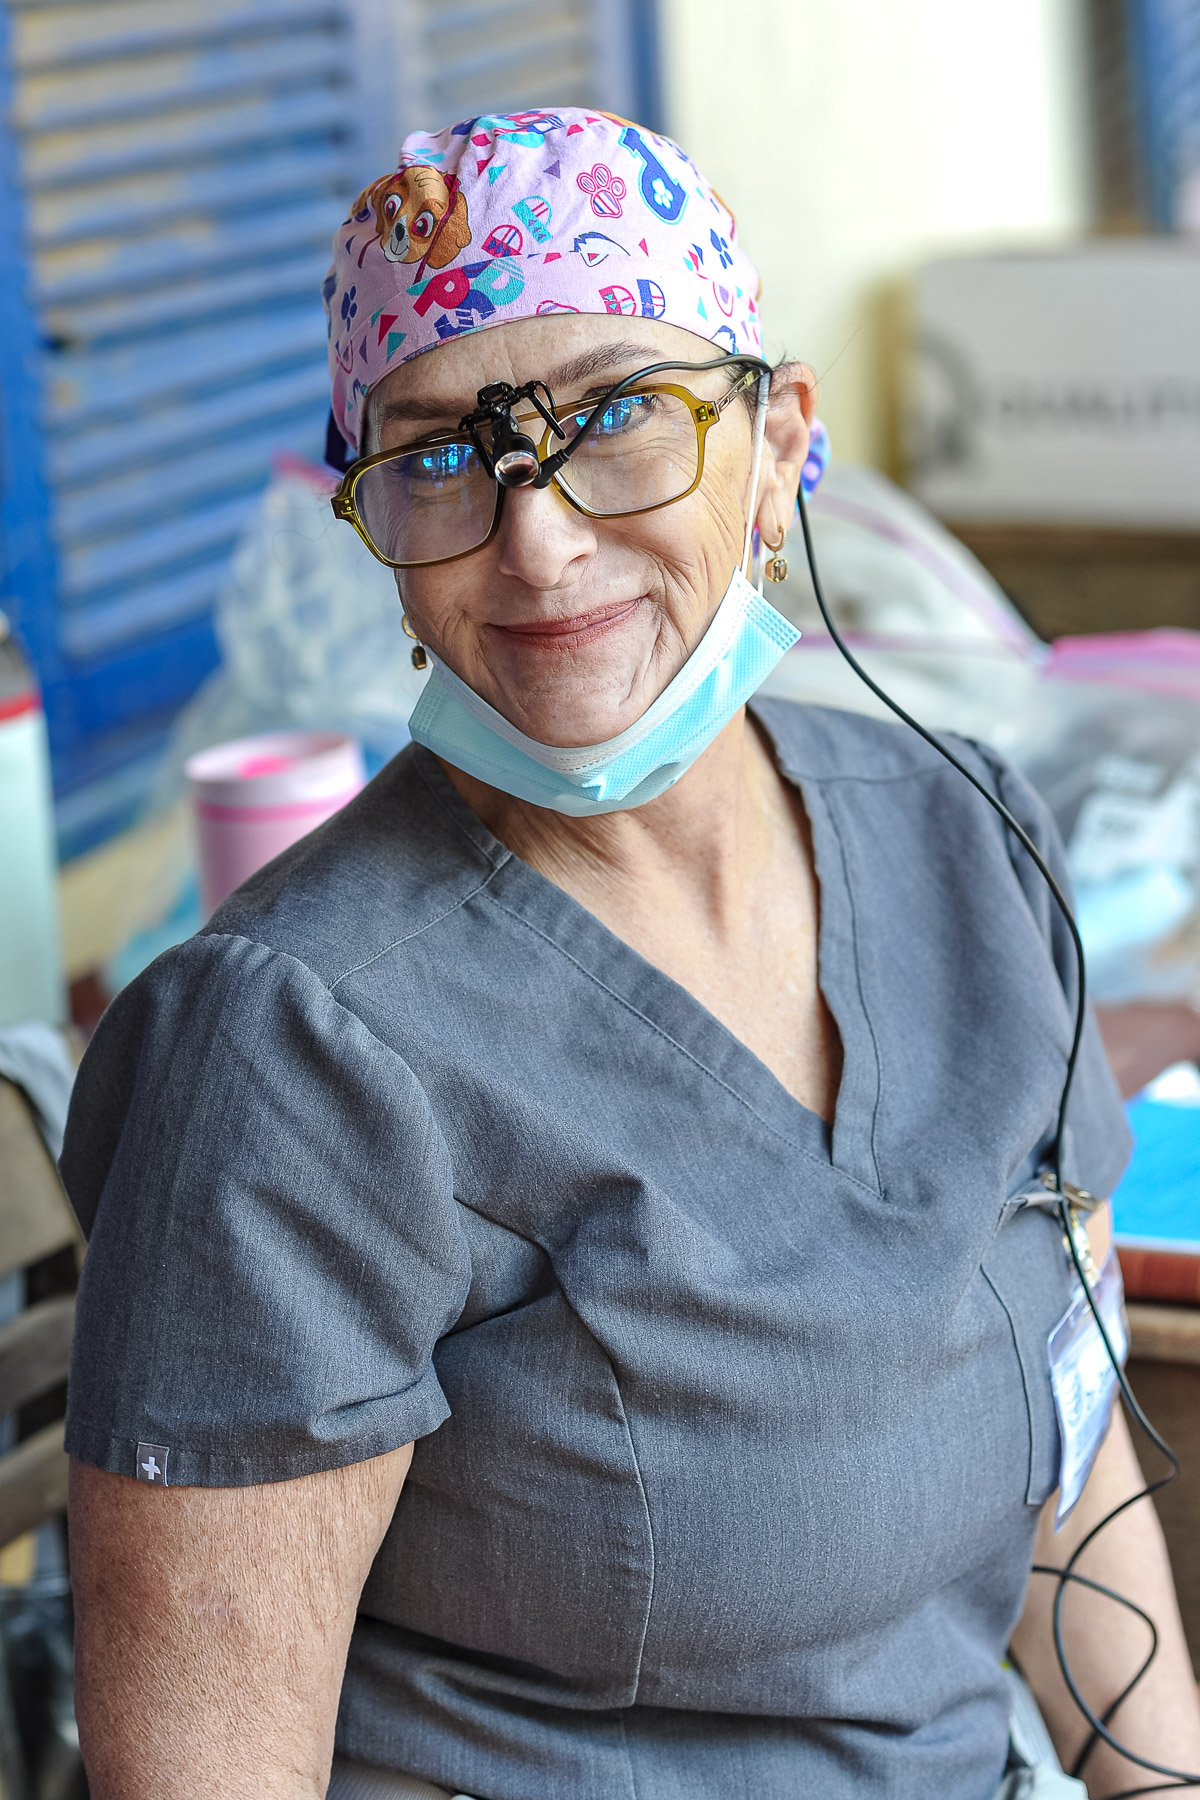









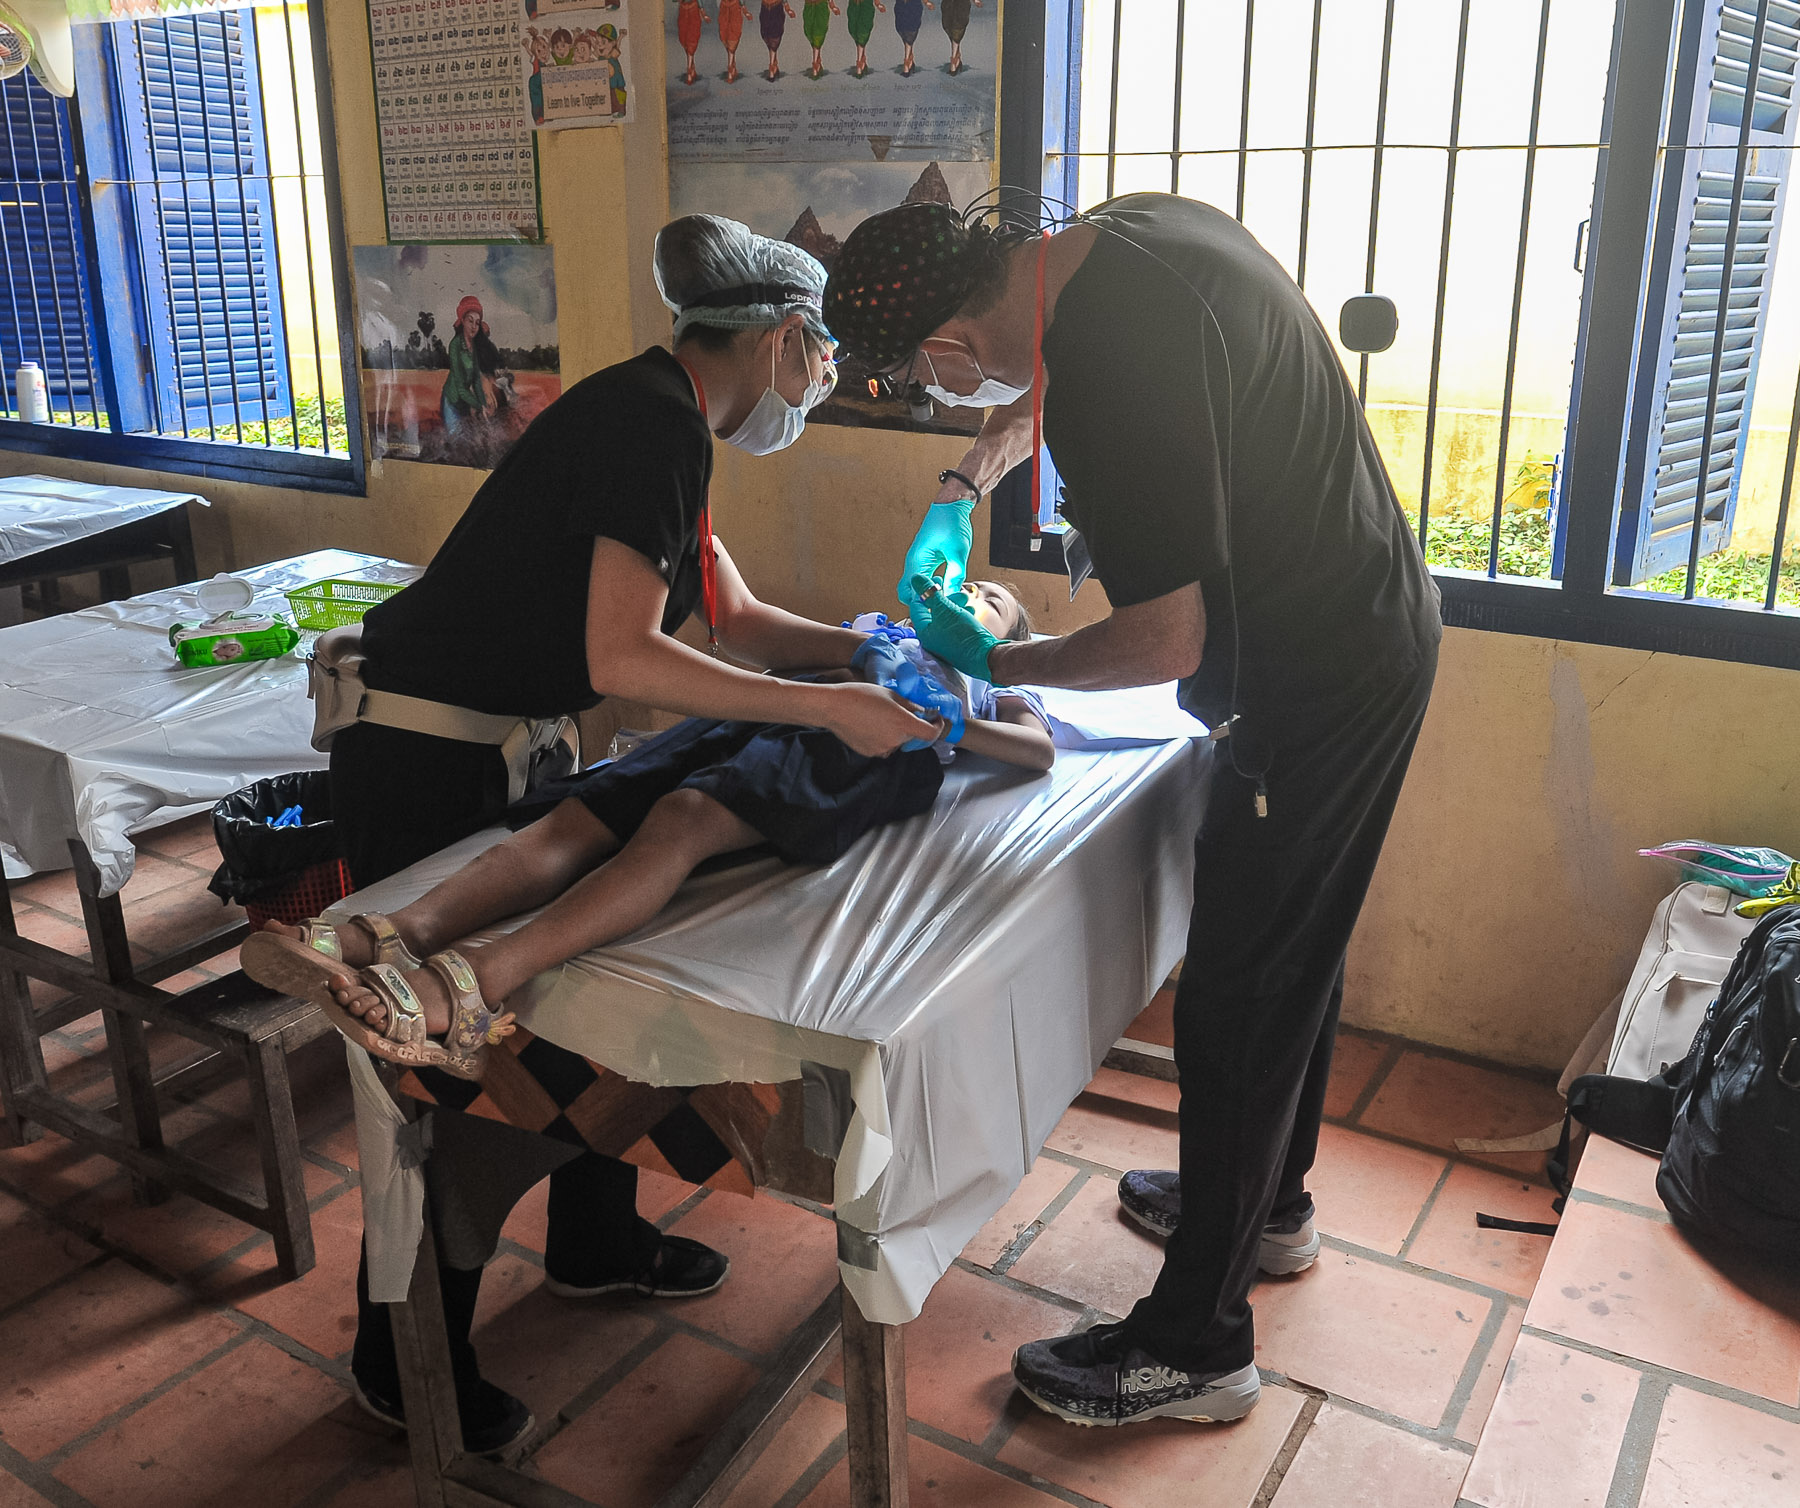


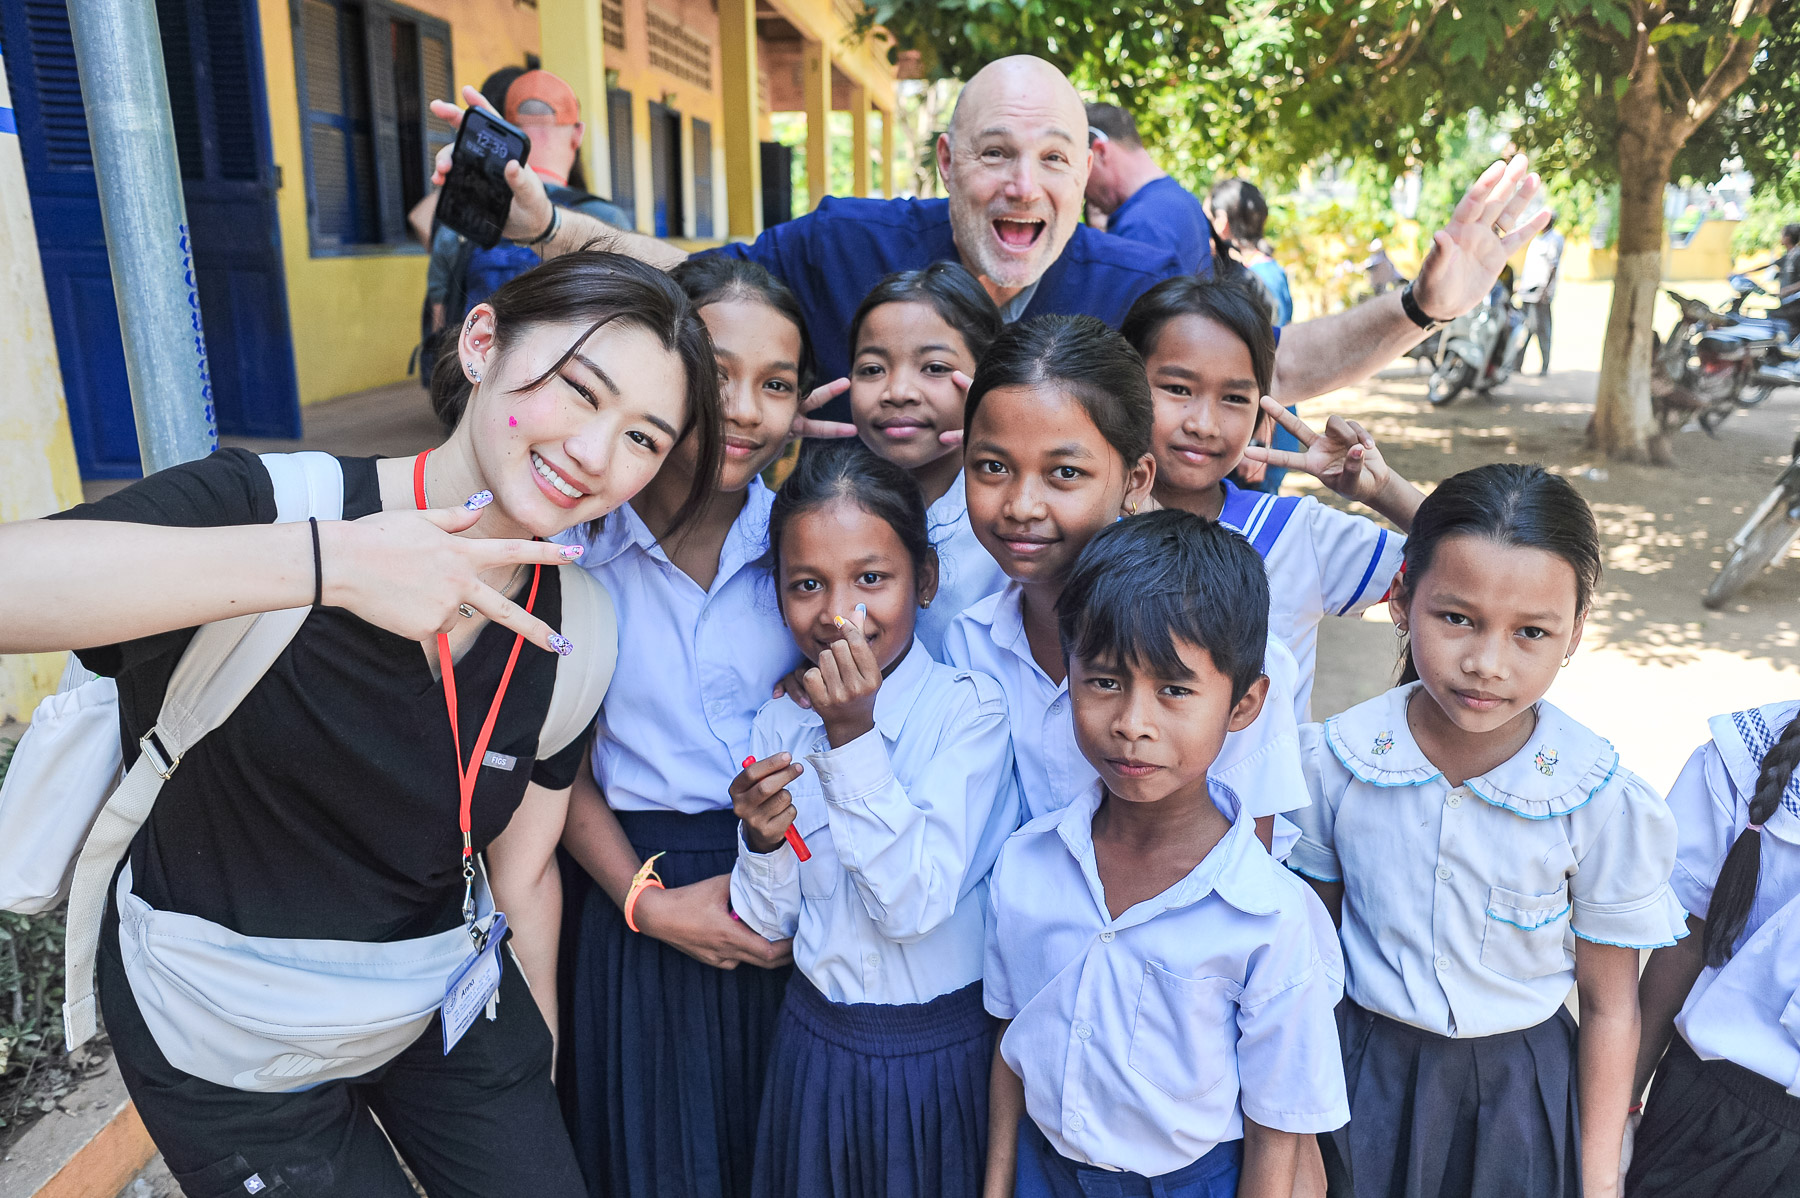











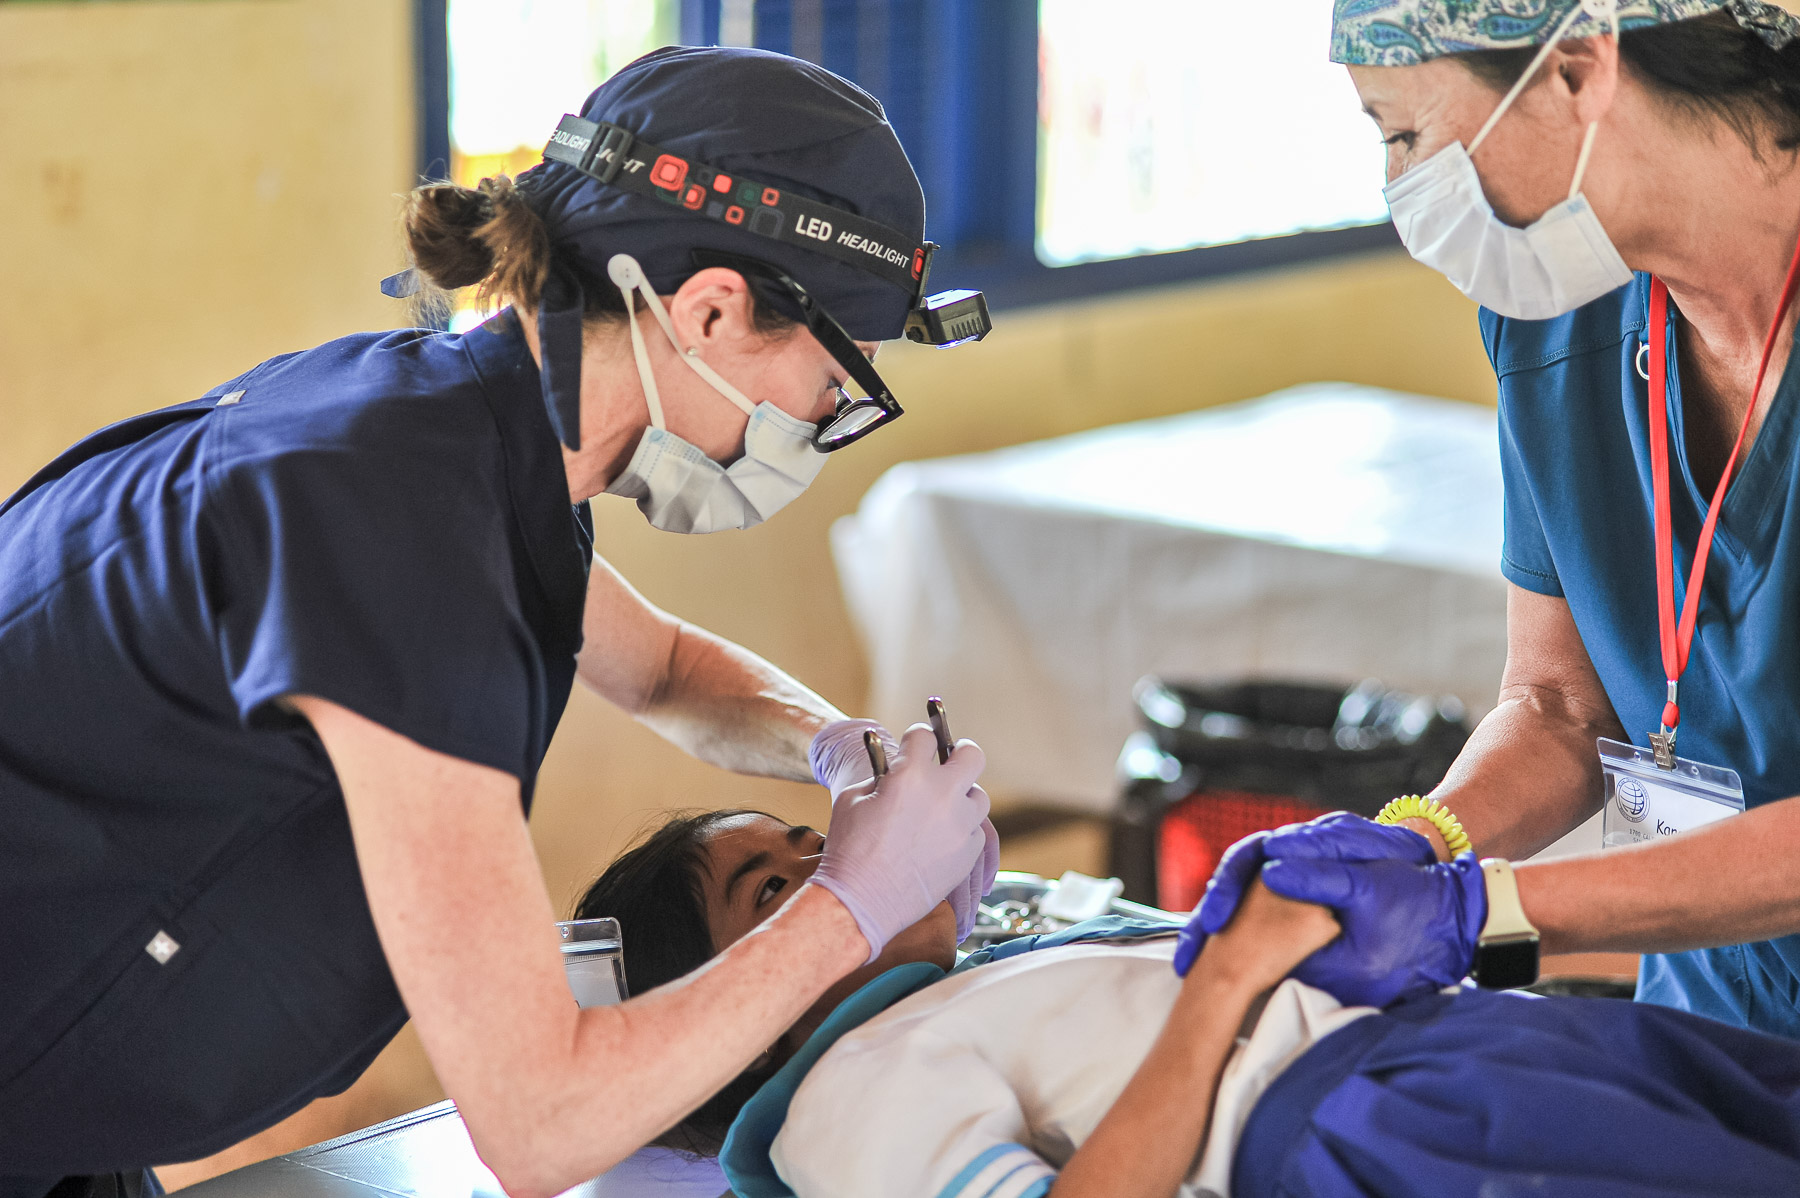


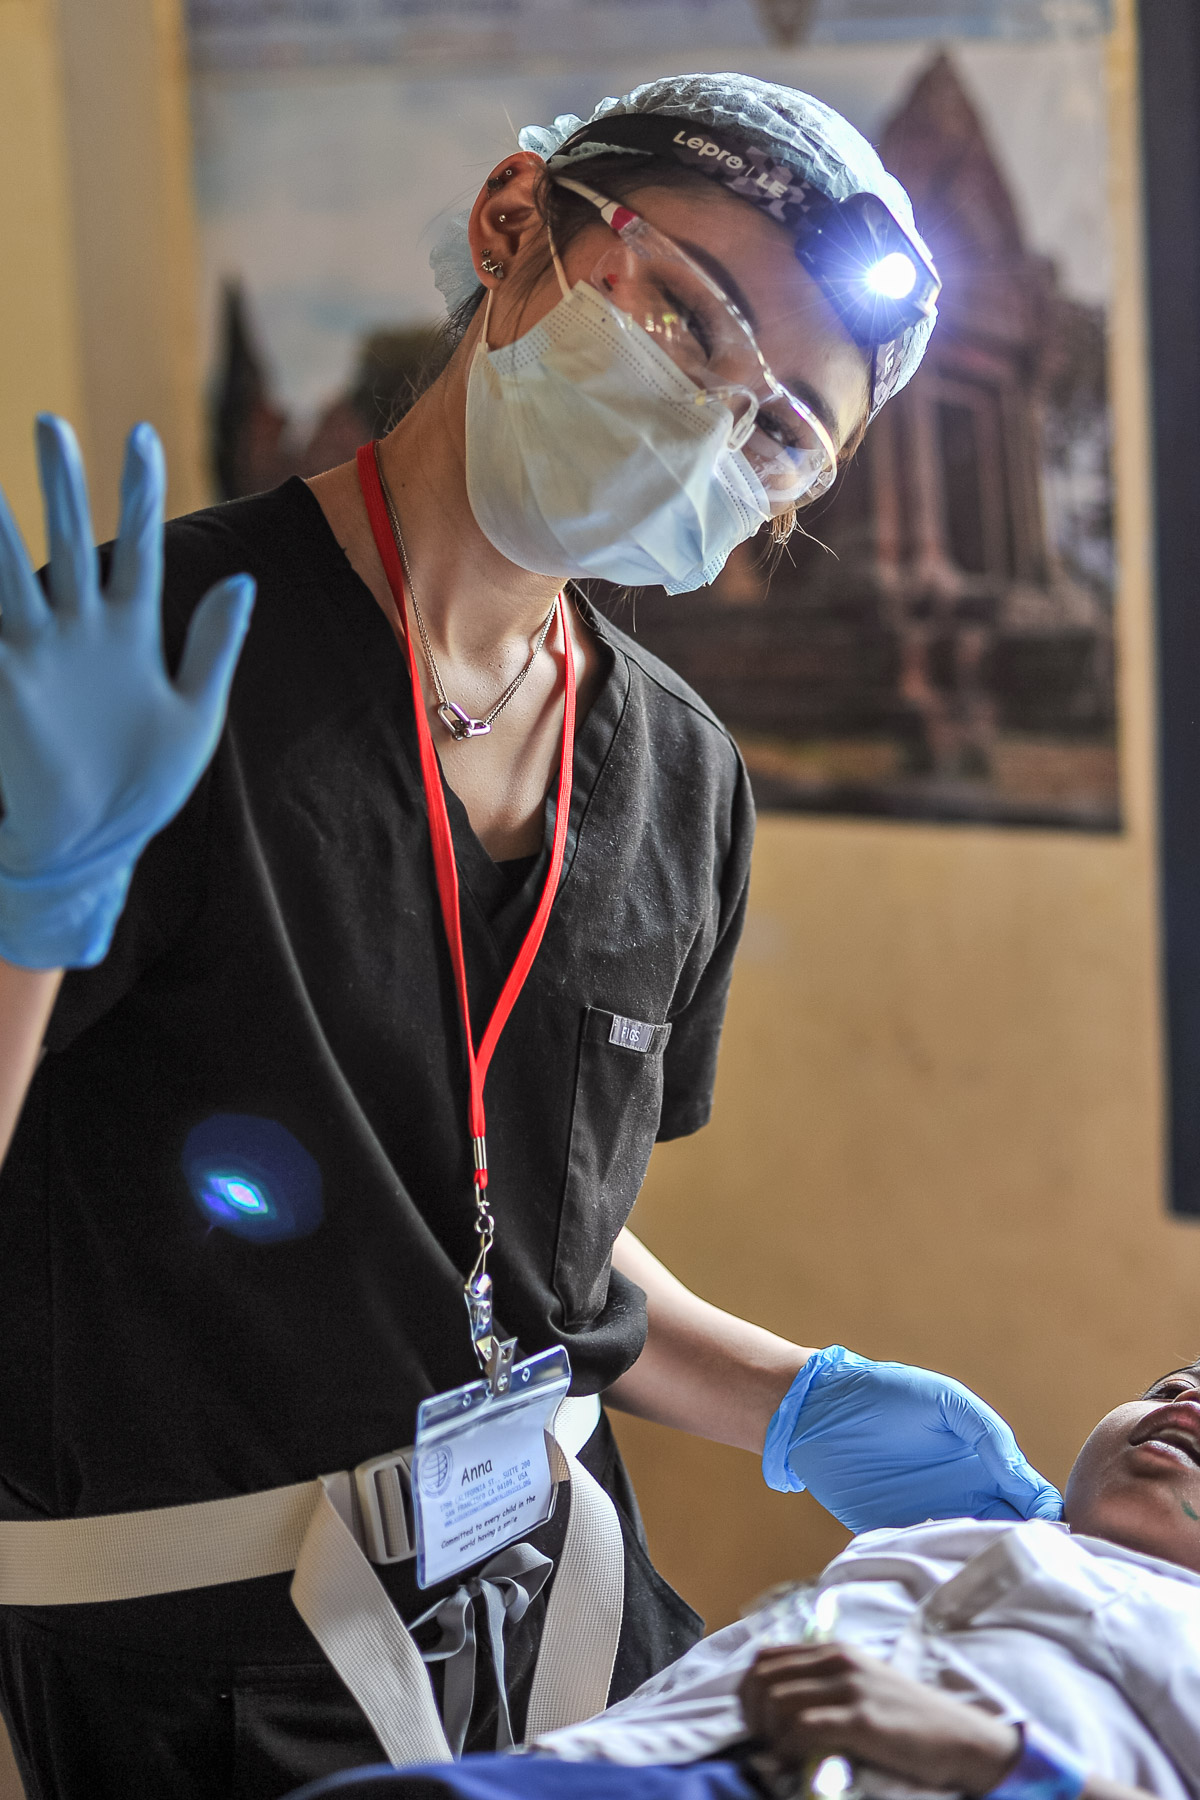









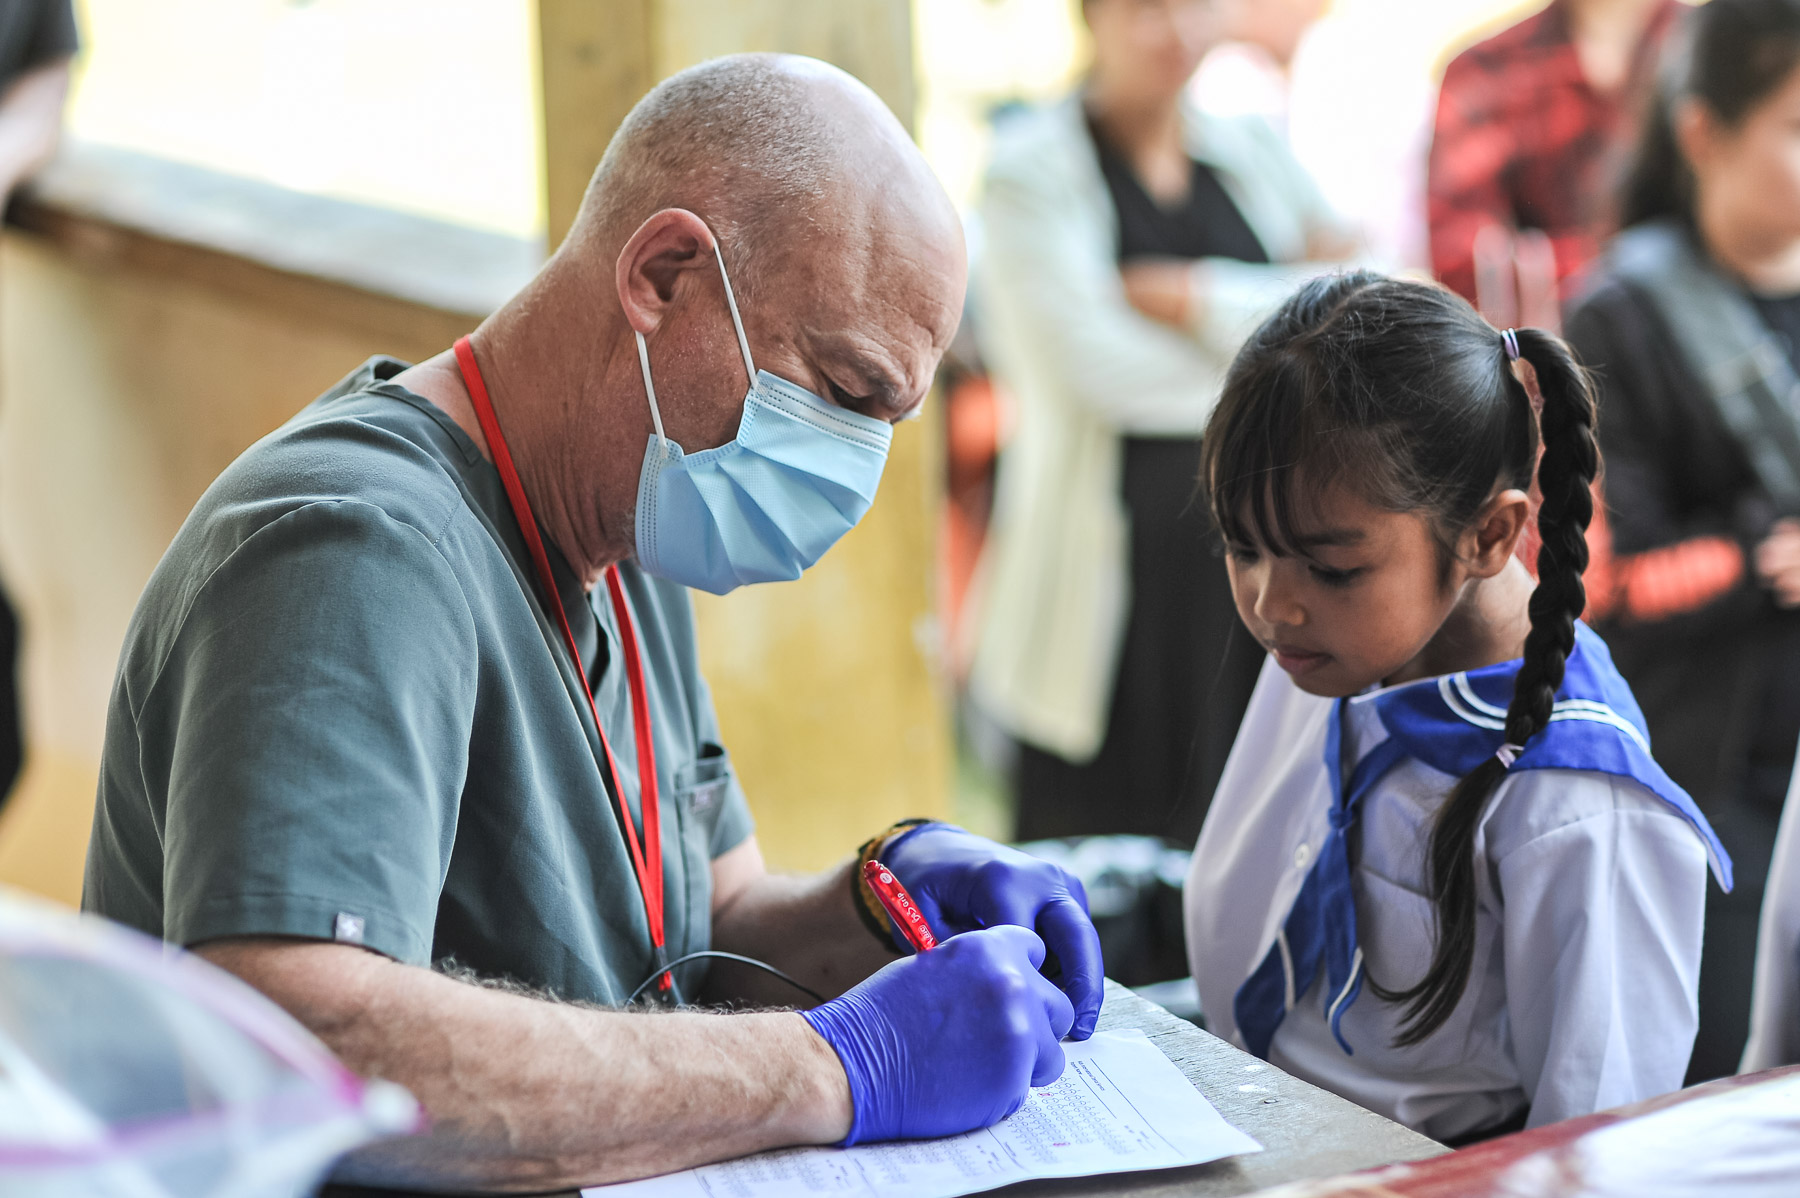







The team photograph records the people assembled for the task. The treatment photographs record their concentration. The portraits remind us who the undertaking was for.
Photographic note: photographs are by Ian Kydd Miller and appear in his published accounts of KIDS’ Cambodian work. Individual capture dates and locations are not supplied for every image. No pictured person has been named from appearance alone.
Sources and further reading
- KIDS: official introduction and charitable identity.
- Stony Brook University: Guatemala outreach, August 2019.
- KIDS: organisational history.
- The Rattle, Spring 2015: Robert Renner profile.
- Agence Kampuchea Presse report, reproduced March 2011.
- Columbia University College of Dental Medicine: Winter 2010 newsletter.
- KIDS: mission and goals.
- Ian Kydd Miller: Cambodian reporting, April 2010.
- People Improvement Organization: 2011 annual report.
- Patch: Cambodia mission report, March 2012.
- Ian Kydd Miller: Why They Come, January 2026.
- Somnang Association: dental partnership, December 2017.
- Australian Dental Association NSW: Dr Marcus Yan biography.
- Ian Kydd Miller: Volunteering with Kids International Dental Services, September 2026.
- Willow Pass Dental Care: humanitarian mission archive.
- KIDS: pandemic update, March 2021.
- KIDS Facebook: posts observed directly, December 2022 and May 2024.
- KIDS: donations and volunteering.
- Phillips Renner Foundation: organisational introduction; its separate tax identity is recorded under EIN 83-4554244.
- US Oral Surgery Management: Wendy Liao outreach announcement, February 2026.
- ProPublica Nonprofit Explorer: IRS-derived KIDS records.
- KIDS: volunteer documentation.
- Ian Kydd Miller: Volunteering with a Camera, September 2026.